Home Blog Page 3

KFF/AP Survey Probes Rural Voters’ Increasing Anxieties About the Rising Cost of Living, Including Health Costs, Heading into the Midterm Elections


rewrite this content and keep HTML tags

Rural voters’ frustrations about the cost of living in their community are growing and appear to be chipping away at Republicans’ enthusiasm to vote as the midterm elections near, a new KFF/Associated Press (AP) Survey of Rural Voters finds.

The survey of more than 2,000 rural voters probes the views and experiences of a group who have been strong supporters of President Trump and Republicans but are feeling economically stressed and facing higher health care costs. The project includes a polling analysis from KFF, which often partners with media organizations on surveys, and reporting from journalists at the AP and KFF Health News. Additional stories drawing on the poll findings and rural voters’ perspectives will come out in the coming weeks.

The survey’s key takeaways include:

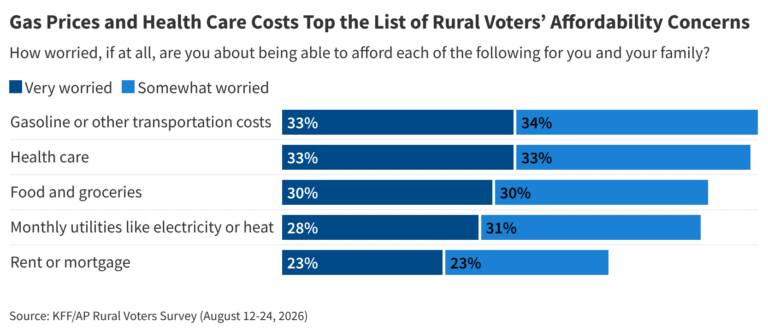
  • Cost of living concerns are increasing, and Republicans maintain an edge with rural voters. Rural voters overwhelmingly name the cost of living as the top issue they want candidates to talk about, and three quarters now rate the cost of living in their area as either “fair” or “poor,” a 25-percentage point increase from 2017. When it comes to household expenses, rural voters worry most about health costs and gas prices. More rural voters prefer the Republican Party than the Democratic Party to best address the cost of living (40% v. 25%), though a quarter (27%), including most independents, trust neither party.
  • Cost of living concerns are increasing, and Republicans maintain an edge with rural voters. Rural voters overwhelmingly name the cost of living as the top issue they want candidates to talk about, and three quarters now rate the cost of living in their area as either “fair” or “poor,” a 25-percentage point increase from 2017. When it comes to household expenses, rural voters worry most about health costs and gas prices. More rural voters prefer the Republican Party than the Democratic Party to best address the cost of living (40% v. 25%), though a quarter (27%), including most independents, trust neither party.
  • Cost of living concerns are increasing, and Republicans maintain an edge with rural voters. Rural voters overwhelmingly name the cost of living as the top issue they want candidates to talk about, and three quarters now rate the cost of living in their area as either “fair” or “poor,” a 25-percentage point increase from 2017. When it comes to household expenses, rural voters worry most about health costs and gas prices. More rural voters prefer the Republican Party than the Democratic Party to best address the cost of living (40% v. 25%), though a quarter (27%), including most independents, trust neither party.
  • Cost of living concerns are increasing, and Republicans maintain an edge with rural voters. Rural voters overwhelmingly name the cost of living as the top issue they want candidates to talk about, and three quarters now rate the cost of living in their area as either “fair” or “poor,” a 25-percentage point increase from 2017. When it comes to household expenses, rural voters worry most about health costs and gas prices. More rural voters prefer the Republican Party than the Democratic Party to best address the cost of living (40% v. 25%), though a quarter (27%), including most independents, trust neither party.

The survey also examines rural voters’ views about job opportunities and safety in their community, who they trust to handle key economic and health care issues, and health care access issues in their communities, including provider and hospital shortages.

METHODOLOGY

Designed and analyzed by public opinion researchers at KFF and the Associated Press, this survey was conducted August 12-24, 2026, online and by telephone among a nationally representative sample of 2,241 U.S. adults registered to vote in rural areas of the country. The margin of sampling error is plus or minus three percentage points for the full sample of rural voters. For results based on other subgroups, the margin of sampling error may be higher. The survey was conducted in English and Spanish.

About KFF

KFF is the independent source for health policy research, polling, and journalism. Its mission is to serve as a nonpartisan source of information for policymakers, the media, the health policy community, and the public. KFF Health News is a national newsroom that produces in-depth journalism about health issues and is one of the core operating programs at KFF.

About the Associated Press

The Associated Press is an independent global news organization dedicated to factual reporting. Founded in 1846, AP today remains the most trusted source of fast, accurate, unbiased news in all formats and the essential provider of the technology and services vital to the news business. More than half the world’s population sees AP journalism every day. Online: http://www.ap.org


Source link

A Closer Look at the $50 Billion Rural Health Transformation Program


rewrite this content and keep HTML tags

Structure

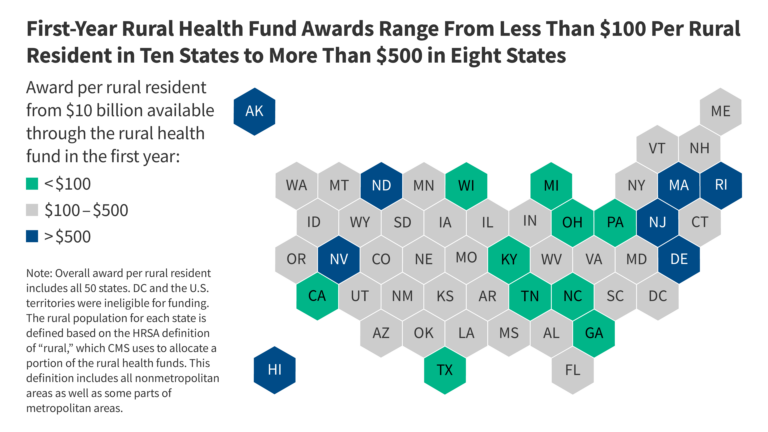
The rural health fund will provide $50 billion in grants to states over five years.

The rural health fund was added to the 2025 reconciliation law as a political compromise just prior to the law’s passage. The fund emerged during Senate negotiations in response to concerns about the impact of federal spending cuts on rural hospitals. Nonetheless, the program is not specific to rural hospitals but instead supports a much broader set of activities (see below). The law specifies that the Centers for Medicare & Medicaid Services (CMS) will oversee the program. It grants the agency substantial leeway to determine how to distribute funding across states and flexibility to expand the permitted uses of funding and determine the terms and conditions. CMS is administering the program through the new Office of Rural Health Transformation.

Under the rural health fund, CMS will award $10 billion in grants to approved states each year from fiscal years 2026 to 2030, a five-year period, for a total of $50 billion. States will be allowed to spend funds that they receive at a given point through the end of the following fiscal year, and CMS will redistribute any unused funds over time, but all funds must be spent by the end of fiscal year 2032. States will administer their programs, subject to terms agreed upon with CMS. However, the funding is occurring through a mechanism known as a “cooperative agreement,” which “require[s] substantial CMS project involvement after an award is made.”  

States had a one-time opportunity to apply for funding and all states were approved, meaning that they are eligible for funding for all five years of the program. However, CMS may withhold, reduce, eliminate, or recover funding over time if it determines that a state is not in compliance with program rules, the state has not made “satisfactory progress,” or that funding is no longer “in the government’s best interest.” The law indicates that there will be no administrative or judicial review of these and other funding decisions made by CMS.

The law and CMS established a fast-paced timeline for states to apply for funding and initiate programs during the first year of the program. CMS issued a Notice of Funding Opportunity in September 2025 with guidance on how to apply. States then had less than two months to prepare their applications. Those applications affect the scope of activities states can engage in and the amount of funding they receive for the life of the program. CMS announced first-year awards in December 2025. States were then given less than a year to finalize their plans through discussions with CMS, develop their own application process for entities within the state to receive funding, process applications, obligate funding, and submit their first annual progress reports (which will affect second-year awards). States likely differ in their capacity to manage procurement processes and have varied widely in terms of how quickly they have distributed funds during the first year.

Key Dates

Enactment and State Applications

  • July 4, 2025: The 2025 reconciliation law is enacted. The law includes large cuts to federal health care spending and the creation of the rural health fund.
  • September 15, 2025: CMS releases Notice of Funding Opportunity that includes guidance on how CMS will administer the program and how states can apply.
  • November 5, 2025: Deadline for states to apply.

First-Year Awards (fiscal year 2026)

  • December 29, 2025: CMS announces awards, totaling $10 billion.
  • Following first-year award announcement: States work with CMS to reconcile their plans with awarded amounts and program requirements and to determine how funds will be apportioned across initiatives, after which CMS makes first-year funding available.
  • August 31, 2026: Deadline for states to submit first of five annual reports.
  • October 30, 2026: Deadline for states to obligate funding.
  • November 29, 2026: Deadline for states to submit first of thirteen quarterly reports.
  • September 30, 2027. Deadline for states to spend first-year awards. CMS will redistribute unused funds in fiscal year 2028.

Second-Through Fifth-Year Awards (fiscal years 2027-2030)

  • October 31 of fiscal year: CMS will announce fiscal year awards totaling $10 billion by this date.
  • September 30 of following fiscal year: Deadline for states to spend awards. CMS will redistribute unused funds in the following fiscal year.

Program Wind-Down

  • February 27, 2031: Deadline for states to submit final report.
  • September 30, 2031: Deadline for states to spend fifth-year awards. CMS will redistribute unused funds in the next fiscal year.
  • September 30, 2032: Deadline for states to spend any remaining dollars redistributed by CMS.
  • October 1, 2032: Unused funds returned to Treasury Department.

The rural health fund is intended to transform the delivery of health care in rural communities and is being used to support a wide variety of activities.

The rural health fund is designed to help “support…rural communities to improve healthcare access, quality, and outcomes through system transformation” according to CMS. CMS also indicated that it “expects States to design initiatives that invest in long-term, sustainable improvements rather than temporary fixes or funding perpetual operating expenses.” States can use funding for eleven purposes detailed in law and through guidance from CMS, with certain restrictions (see textbox below and Appendix Table 1). CMS has also identified five strategic goals of the program that align with these uses: make rural America healthy again, sustainable access, workforce development, innovative care, and tech innovation (see Appendix Table 2).

In line with the broad scope of the rural health fund, states are implementing a wide variety of activities under the program. For example, states are using funds to promote prevention and chronic disease management interventions, support collaboration among rural health care facilities (such as by sharing administrative services) and between rural providers and regional health systems, recruit clinical workers to rural areas, promote technological advancements (such as by expanding telehealth or promoting AI diagnostic tools), invest in existing hospital buildings and infrastructure, help hospitals determine which services should and should not be maintained, and support the adoption of value-based care and alternative payment models.

Specific state examples include the following (each state is undertaking multiple initiatives):

  • Alabama is funding the use of telerobotics to provide ultrasounds remotely.
  • Alaska is funding the use of drones to deliver medications to remote areas.
  • California is funding new provider collaboration networks, connecting regional hospitals with critical access hospitals, clinics, birthing centers, and other providers.
  • Michigan is funding an initiative to bring “services closer to where people work and live,” such as by “expanding…home-based care for older adults to allow them to age in place.”
  • North Carolina is increasing access to healthy foods, such as by “facilitat[ing] farm-to-hospital [programs], mobile food markets, and community-based food access.”
  • Montana is helping rural hospitals “right size” their services, which could entail eliminating some service offerings to improve hospitals’ financial sustainability.
  • Nevada is funding an expansion of its rural workforce, such as through provider recruitment incentives.

Permitted Uses

States must use funding for at least three of the following permitted uses.

  • Promote consumer tech solutions. For the prevention and management of chronic diseases. Examples include remote patient monitoring (e.g., through wearable devices), apps that connect patients with providers and health information, and digital health tools in community access points. States can also provide seed funding for innovative, high-impact tech solutions through a Rural Tech Catalyst Fund, subject to spending restrictions.
  • Support IT advances. Such as by expanding access to telehealth, upgrading or replacing electronic health record systems (replacements are subject to spending restrictions), facilitating health information exchange and interoperability, enhancing cybersecurity, and promoting artificial intelligence for clinical and administrative uses.
  • Provide training and technical assistance for technology that improves care delivery in rural hospitals. Such as for “remote [patient] monitoring, robotics, artificial intelligence, and other advanced technologies.”
  • Recruiting and retaining clinical workers. Such as by promoting health careers among local high school students, developing new residency and fellowship programs, offering advanced training for clinical workers, and providing tuition reimbursement or other incentives. Clinical workers who directly benefit must commit to serve rural areas for at least five years.
  • Improving prevention and chronic disease management. Such as through screening and early detection (e.g., mobile cancer screening), nutrition education, improving access to healthy food and to outdoor activities, early maternal and infant interventions (e.g., home visits), and care management programs.
  • Matching service offerings to local need. Such as by expanding access through telehealth, mobile units and satellite sites, strengthening emergency medical services, and providing non-medical transportation. This could also include “right sizing” delivery systems by eliminating services that cannot be sustained.
  • Paying providers for health care items or services. Provider payments are subject to a number of restrictions: they cannot exceed 15% of a state award in a given budget period, be used for short-term relief, supplement or duplicate existing funding sources (including Medicaid), or cover gender-affirming care or most abortion services. Examples of permitted uses include incentive payments for providers to improve quality or reduce costs.
  • Supporting innovative models of care. Including value-based care arrangements and alternative payment models. Such as by helping providers participate in the Achieving Healthcare Efficiency through Accountable Design (AHEAD) model (which, among other things, replaces traditional hospital reimbursement from multiple payers with global budgets for a given facility).
  • Investing in existing health care facility buildings and infrastructure. Investments cannot exceed 20% of a state award in a given budget period and cannot be used for new buildings or equipment. Examples include repairing existing buildings and equipment, minor renovations, interior modifications, upgrading lighting and electrical systems, and installing or upgrading security systems.
  • Fostering collaboration among providers. Such as through hub-and-spoke models (which connect anchor facilities, like larger regional hospitals, with local “spokes,” like clinics and small rural hospitals), shared services or group purchasing (e.g., of administrative services), or clinically integrated networks (groups of providers that join together to improve care and reduce costs without formally merging).
  • Supporting access to behavioral health care services. Such as through telehealth options, substance use disorder and opioid treatment, Certified Community Behavioral Health Clinics, and mobile crisis teams and centers.

States may also use up to 10% of their award in a given budget period on administrative expenses. Program restrictions listed above are not comprehensive.

Uses for Hospitals

Rural health funds are not just for hospitals, and there are restrictions on how hospitals can benefit.

While the fund emerged in response to concerns about the impact of the reconciliation law on rural hospitals, the extent to which it will benefit these facilities is unclear. States can choose how much of the funds will go to hospitals versus other rural providers and various other entities, such as contractors providing technical assistance, universities participating in workforce initiatives, regional health systems in urban areas collaborating with rural providers, and vendors developing new health technologies. Of the dollars going to rural hospitals, it is not yet clear which specific facilities will receive funding and the extent to which states will target resources to particular types of hospitals, such as those that are isolated or in financial distress. Additionally, hospitals that are not in rural areas can also receive funding, as long as it is to the benefit of rural communities and residents.

Initiatives could benefit hospitals to varying degrees. For example, uses of the funds that could more directly benefit hospitals include investing in existing hospital infrastructure (permitted within limits), strengthening collaboration among rural facilities and other providers, and supporting alternative payment models. Other initiatives, such as programs to promote health literacy and healthy behaviors, may have less direct or no obvious benefits for hospitals. The benefit to rural hospitals—and to other providers, patients, and rural communities—will also depend on how effective state initiatives are, which is difficult to predict. 

While funding could benefit hospitals in a number of ways, there are also limitations on how it can do so. For example, CMS guidance indicates that rural health funds cannot be used for:

  • Propping up struggling hospitals with temporary relief. The funds are not intended “to be used for perpetual operating expenses, but rather for investments…that will have sustainable impact beyond the end of the program,” according to CMS.
  • Payments to providers for care that exceed 15% of a state award in a given budget period. Payments to providers must be related to the strategic goals of the program, such as bonus payments for providing high-quality care, and cannot be used to supplement or duplicate existing funding, including payments from Medicaid or private insurance.
  • Construction, building expansion, or purchasing buildings, though they can be used for certain investments in existing rural health care facility buildings and infrastructure, not to exceed 20% of a state award in a given budget period.
  • Replacements for previous HITECH-certified electronic medical record (EMR) systems that exceed 5% of a state award in a given budget period.
  • Funds for gender-affirming care (a limitation that is not restricted to care for minors, as are many other federal measures) and reimbursement for most abortion services. There are also limitations related to “citizenship documentation requirements for payments made with respect to an individual.” Many hospitals do not currently collect patient immigration status but may need to do so to be reimbursed for patient care with rural health funds.

The rural health fund may help hospitals adapt to the loss of federal funding under the reconciliation law, though the extent to which it will do so is unclear. The reconciliation law made historic reductions in federal support for health care and is expected to result in an unprecedented increase in the number of people without health insurance. An increasing uninsured rate results in fewer patients with health coverage for hospital care, and an increase in the amount of uncompensated care hospitals provide. At the same time, the 2025 reconciliation law made significant changes to Medicaid financing that could result in major reductions to the rates Medicaid pays for hospital services in most states.

Just as it is unclear how much hospitals will benefit under the rural health fund, it is also hard to predict how much hospitals will lose due to spending cuts under the reconciliation law. As detailed below, the rural health fund is smaller than estimated cuts to federal Medicaid spending when looking at rural areas in aggregate, and most of the cuts will persist over time, in contrast to the rural health fund.

The hospital industry and some members of Congress have called for a greater focus on hospitals. The hospital industry has recommended that the rural health fund give greater priority to supporting rural hospitals, including by lifting restrictions on provider payments and capital investments. A group of Senators also recommended that the program focus more on rural hospitals and other rural providers and expressed concern that small rural providers will have a harder time vying with larger systems and organizations for funding. Increasing funding for rural hospitals would do more to address concerns about the financial standing of these facilities, an original motivation for the program, but would involve tradeoffs with competing initiatives.
Source link

Survey: Adults With Multiple or Complex Health Conditions Face Significant Challenges with Health Costs and Commonly Struggle to Access Care 


rewrite this content and keep HTML tags

Adults with multiple or complex health conditions, who already face unique physical and mental challenges, commonly struggle to pay their medical bills and access needed care and medication—challenges that fall hardest on uninsured adults, according to a new KFF survey of more than 25 thousand adults. A companion Beyond the Data column by KFF Founding President and CEO Dr. Drew Altman explores the survey’s findings about uninsured adults with greater health needs and considers why the national discussion of the affordability crisis has largely ignored this group.

“If the first obligation of a health care system is to take care of the sick, we are failing that test. Cost and access problems are hitting the chronically ill hard, and the chronically ill and uninsured especially hard,” said Dr. Drew Altman.

The survey’s large sample size allowed KFF analysts to examine the experiences of adults with certain serious health conditions—including cancer, lung disease, diabetes, cardiovascular disease, or a mental health condition—as well as those managing care for multiple health problems.

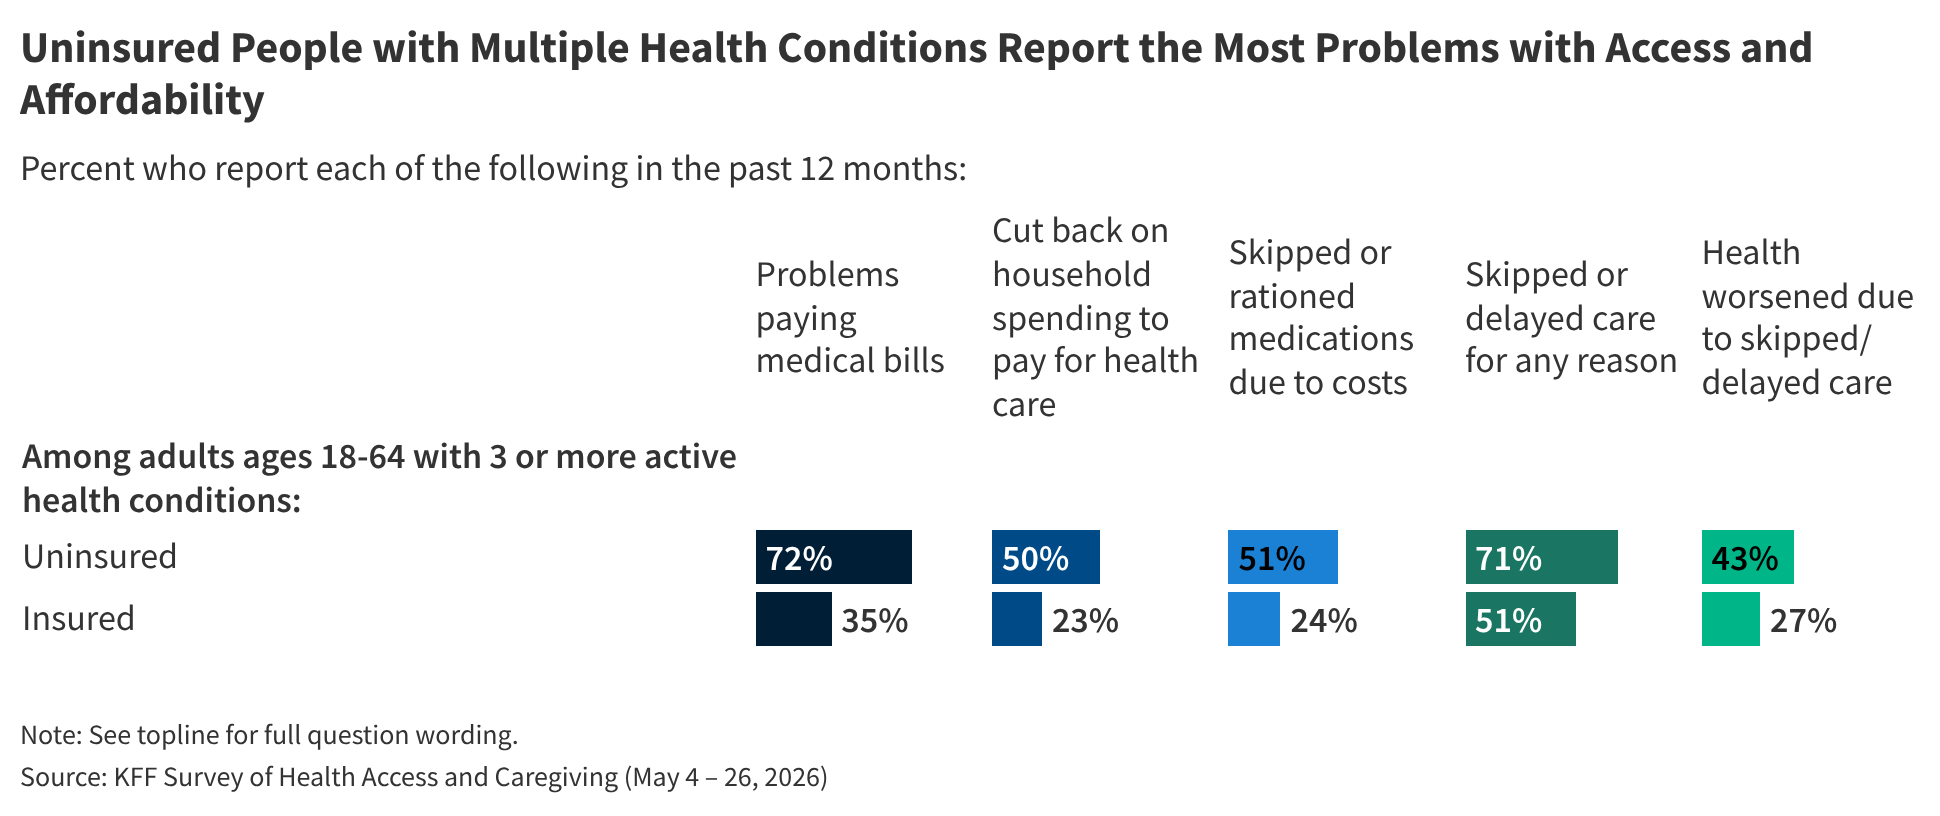
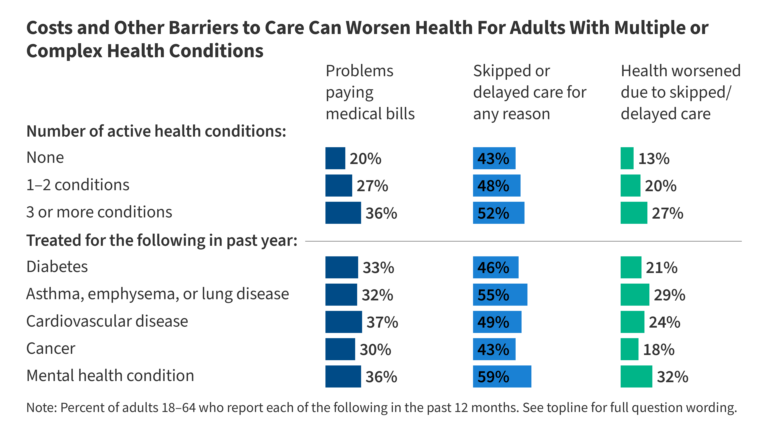
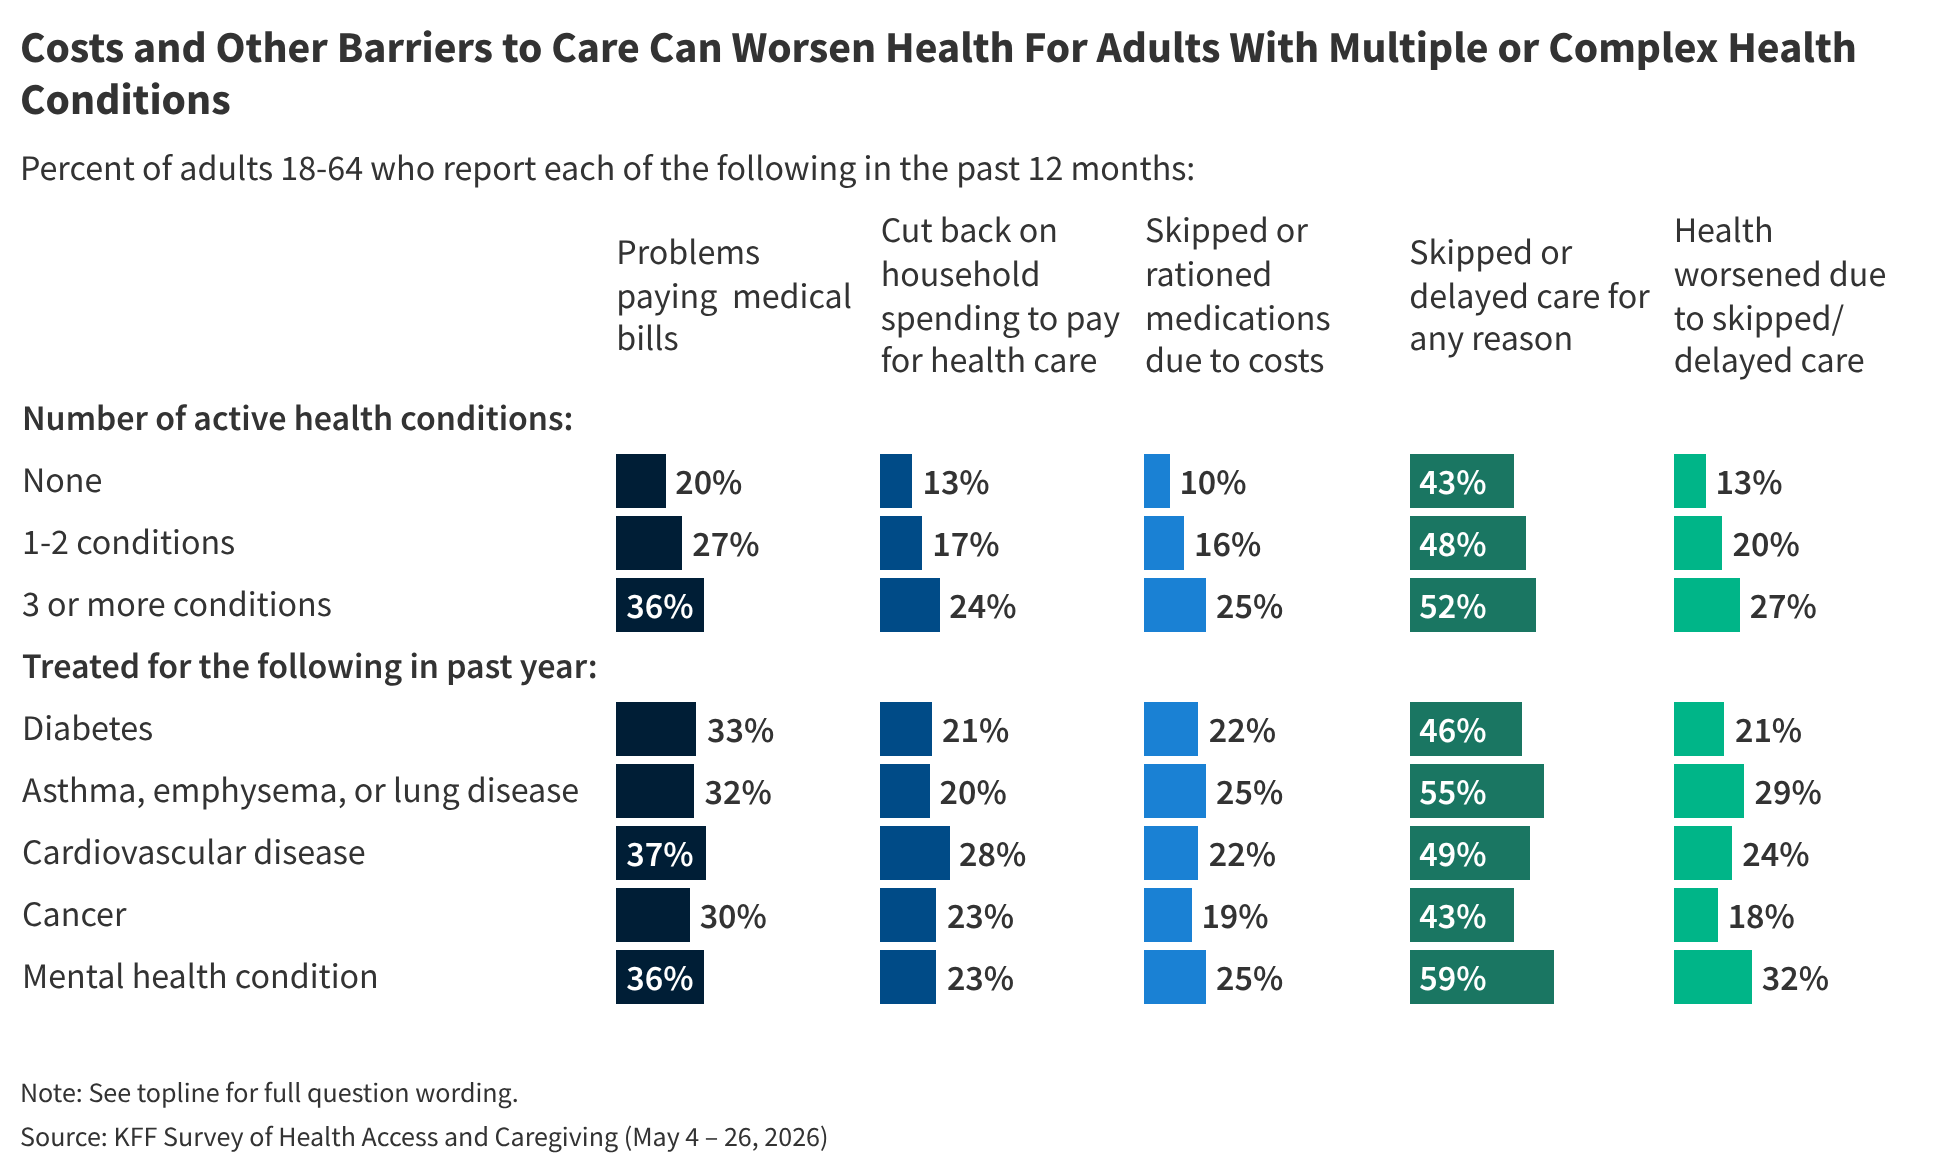
About a third of adults ages 18-64 with multiple or certain complex health conditions say they struggled to pay or could not pay their medical bills in the past year. Adults with three or more conditions (36%), those with cardiovascular disease (37%), and those with a mental health condition (36%) are particularly likely to report struggling with medical bills. As part of these affordability challenges, about a quarter of adults with three or more conditions say they have had to cut back on household expenses to cover medical costs, compared to just about 1 in 10 of those without active health conditions.

High health costs can create major barriers to care, sometimes determining who is able to access the treatments and medications they need. About half of adults with three or more health conditions say they skipped or delayed care in the past year, including about 1 in 3 who did so due to cost. About 1 in 5 or more adults with multiple or complex health conditions also report not taking their medications as prescribed because they could not afford the cost.

Skipping or delaying care can have serious consequences. Substantial shares of adults across health conditions say their health got worse because they skipped or delayed care, including about 3 in 10 of those with a mental health condition (32%) or lung disease (29%), one quarter of those with cardiovascular disease (24%), and about 1 in 5 of those with cancer (18%) or diabetes (21%).

In addition to challenges with costs, insured adults with greater health needs commonly encounter insurance coverage delays or denials—problems that occur across specific health conditions. About half of insured adults ages 18-64 with three or more conditions say their insurer denied or delayed coverage for a service, treatment, or medication their doctor prescribed, as do about 4 in 10 or more insured adults with certain complex conditions, including diabetes (38%), lung disease (43%), cancer (43%), cardiovascular disease (45%), or a mental health condition (47%).

Uninsured Adults Struggle the Most to Afford and Access Care
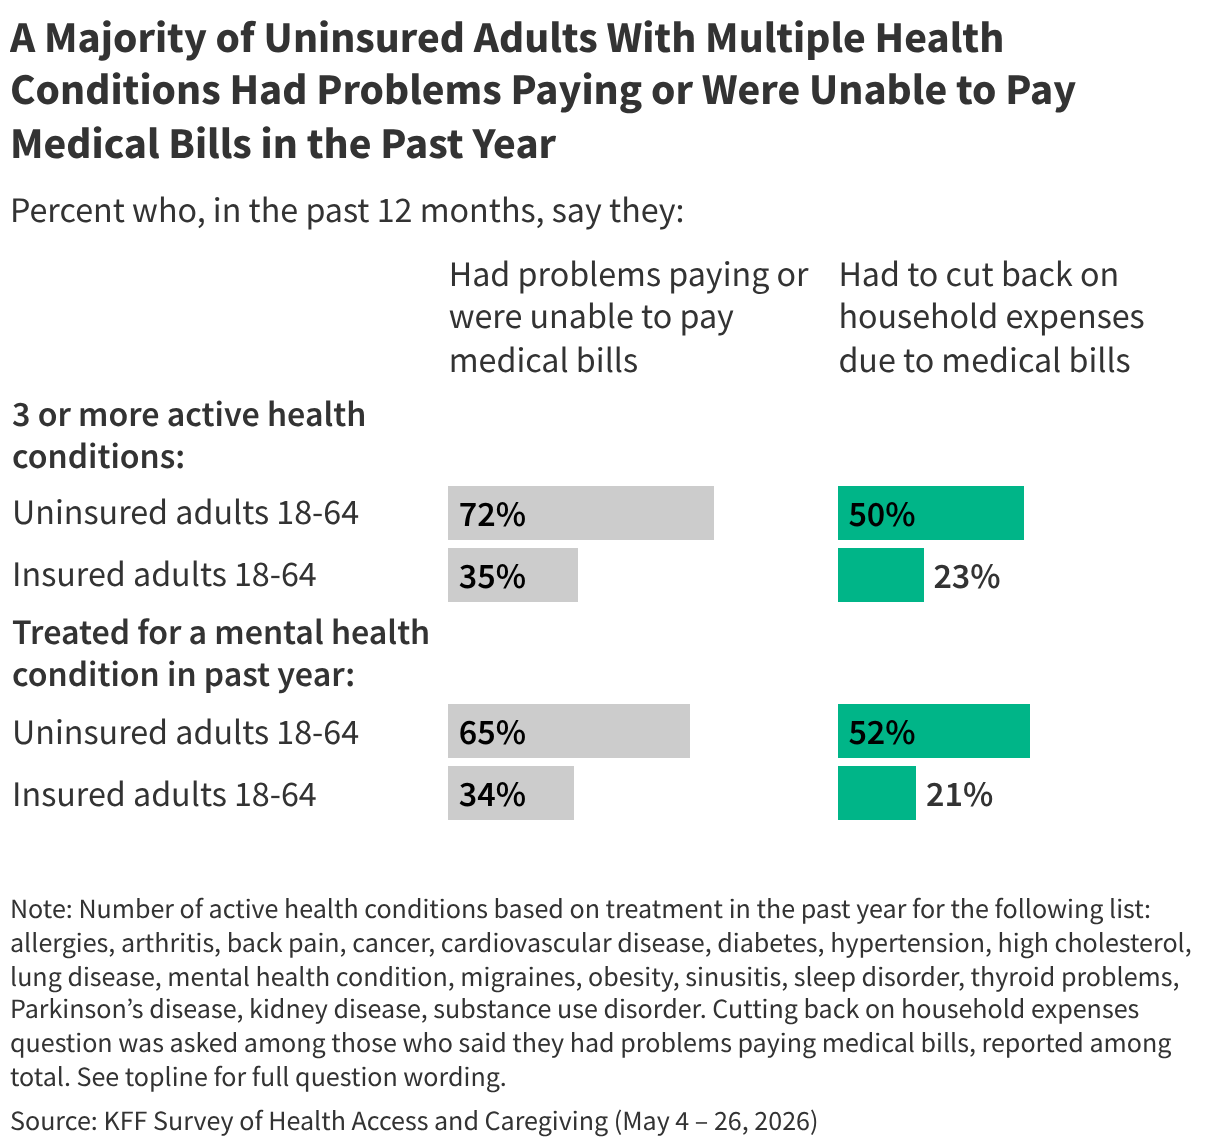
As Drew Altman writes in his new column, health care affordability is most challenging for uninsured adults with multiple health conditions—most of whom say they struggle with medical bills (72%) and half of whom say they cut back on household spending to cover their health costs. Uninsured adults with three or more health conditions are twenty percentage points more likely than their insured counterparts to say they skipped or delayed needed care in the past year (71% vs. 51%). They are also about twice as likely as those who are insured to say they did not take their medication as prescribed due to cost (51% vs. 24%).

For uninsured adults, going without needed care and medications may carry even greater risks that worsen existing barriers to care. Untreated health conditions can worsen over time and become more difficult and costly to treat. Among uninsured adults, about 4 in 10 with multiple conditions (43%) and about half with a mental health condition (47%) say their health got worse after skipping or delaying care—making them about one and a half times as likely as their insured counterparts to experience a decline in health.

Other findings about older adults (aged 65+) with multiple and complex health conditions are available in the full report.

Dr. Altman will discuss KFF’s findings about chronic health conditions and the broader health policy landscape in his keynote address at the National Academy of Medicine’s Annual Meeting in October.

Designed and analyzed by KFF public opinion researchers, KFF’s Survey of Health Access and Caregiving was conducted in English and in Spanish May 4 – 26, 2026, online and by telephone among a large, nationally representative sample of 25,873 adults, including 16,677 who say they have received treatment for at least one serious or complex health condition in the past year. The margin of sampling error is plus or minus one percentage point for the full sample. For results based on other subgroups, the margin of sampling error may be higher.


Source link

The Group that Struggles the Most in American Health Care


rewrite this content and keep HTML tags

There are more than enough needs to go around in American health care, but if I had to pick the one group that struggles the most with costs and access, it would be people with chronic illnesses who are also uninsured. These are people with cancer or heart disease or diabetes or mental health conditions, or multiple chronic health problems, who also don’t have insurance coverage. We don’t have an exact count of the number of people with multiple medical conditions who are uninsured, but we can say it’s millions of people: about a quarter of the uninsured report that they have been treated for one or two health conditions over the past year and 1 in 10 for three or more conditions. There are about 27 million uninsured people in the U.S., and that number is projected to grow into the low 40 millions when the cuts in federal funding for Medicaid and ACA coverage fully kick in (unless they are reversed).

You could say that’s no surprise—people with multiple conditions use the most care, so they experience greater problems getting and paying for care; that result is so expected in our health system it’s almost tautological to treat it as a discovery. Fair enough, no tenure for me. You could also say that the first obligation of any health system is to take care of people who are sick; it’s a leading indicator of a health system that isn’t working as it should.

Here are a few of the numbers and a chart from a new survey of over 25,000 adults focusing on the chronically ill, which we’ll release tomorrow:

  • Seventy-two percent of adults with multiple health conditions who are uninsured had problems paying for their care or could not pay their medical bills in the last year.
  • Fifty percent had to cut back on other household needs as a result.
  • Sixty-eight percent skipped care because of costs over the last year.

These are about double the already very high rates experienced by people with conditions like cancer, heart disease, diabetes and mental health issues who have insurance. (The chronically ill with insurance experience cost and access problems at rates that are much higher than people who are generally healthy and use less health care).  

And when they need care, the chronically ill uninsured rely on emergency rooms three times as often as their insured counterparts do.

Split bar chart showing share of adults who say they had problems paying or where unable to pay medical bills or they had to cut back on household expenses due to medical bills in the past 12 months. Reported among insured and uninsured adults with 3 or more active health conditions and adults who were treated for a mental health condition in the past year.

Looking at the chronically ill uninsured as a research grouping enables us to examine what’s happening in the health care system more broadly, in this case to people with serious medical problems without insurance. There is no Association for the Multiply Chronically Ill Uninsured on K Street in Washington, D.C., and they don’t have their own powerful advocacy group working on their behalf, although the big disease groups in D.C. have combined forces to advocate for Medicaid and the ACA, which provide coverage for constituents who otherwise would be uninsured. Most of the members of these groups, however, have insurance coverage and advocacy and lobbying focuses on the problems they face paying for and getting care and the drugs they need, including the problems people with significant illnesses have navigating the health insurance system, such as their encounters with prior authorization review. People tell us in polls that prior authorization review is their top concern after costs in health care. The uninsured, of course, would feel lucky to have that problem.

There has been substantial discussion of the chronically ill in health care for years. In October, I’m delivering the keynote address at the annual meeting of the National Academy of Medicine, which is focused on chronic disease. However, most of the discussions to date have focused on prevention and disease management, including better delivery and payment models. Almost none have focused on the fact that when it comes to the “affordability crisis” driving the national discussion of health care today, the chronically ill, and most of all the chronically ill uninsured, are the tip of the spear. 

View all of Drew’s Beyond the Data Columns


Source link

2027 ACA open enrollment: What’s changing


rewrite this content and keep HTML tags

The ACA (Affordable Care Act) open enrollment period for plan year 2027 begins November 1, 2026, in most states – and for people who buy their own health coverage, this year’s enrollment period comes with a number of important changes.

Insurers are leaving the Marketplace in more than 20 states, premiums are rising substantially in many areas, and federal rules have changed who will qualify for subsidies and how much consumers will pay out of pocket. There are also changes to Marketplace platforms, state-funded subsidies, HSA contribution limits, and Catastrophic plan eligibility.

Whether you already have Marketplace coverage or are shopping for a plan for the first time, you’ll want to carefully compare your 2027 options during open enrollment. Here’s a look at the key changes to know before you enroll.

Insurers are entering and exiting the Marketplace

As is always the case, insurers are joining the Marketplace in some areas, and others are exiting the Marketplace. For 2027, there are far more exits than entries.

  • Who’s affected? Hundreds of thousands of Marketplace enrollees have plans that will be terminated at the end of 2026 because of carrier exits. But in some states, many enrollees will have access to new plans due to a carrier entry.
  • What can you do? Carefully compare the plan options available to you during open enrollment. Don’t rely on auto-renewal. If your Marketplace plan is ending, the auto-renewal process will use an algorithm to pick a new plan for you, and it’s in your best interest to pick your own replacement plan. If new plans will be available in your area, comparison shopping during open enrollment will help you know whether any of those plans (or any other available plan) might be the best option for you.

What you need to know if your insurer is exiting the market.

Premiums will be higher on average, subsidies will also be larger

Nationwide, the median proposed rate increase (the midpoint of insurers’ proposed increases) for individual-market policies is about 15% for 2027. This means that roughly half of Marketplace insurers have proposed increases above 15% and the other half have proposed increases of less than 15%. The weighted average proposed increase (which accounts for how many people are enrolled in each insurer’s plans) ranges from under 7% in Vermont, Iowa, and Utah to 29% in Arizona.

But those increases are for full-price premiums, and most individual-market enrollees do not pay full price. The majority of people with individual-market coverage buy it through the Marketplace (as opposed to off-exchange). And 87% of Marketplace enrollees were receiving premium subsidies at the start of 2026.

Subsidy amounts are based on the cost of the second-lowest-cost Silver (benchmark) plan. When the benchmark plan’s premium increases, subsidies also increase. Many enrollees will be fully or partially insulated from the rising premiums, due to increases in their subsidy amounts. But the benchmark plan’s premium change won’t be the same as other plans’ premium changes, and people who don’t get a subsidy (including everyone who buys coverage outside the exchange) will bear the full brunt of the rate increases.

  • Who’s affected? More than 19 million people had Marketplace coverage as of early 2026, and the proposed rate increases also apply to off-exchange plans (where there are no subsidies available to offset the rate increases).
  • What can you do? Pay close attention to the renewal notices you get from your insurer and the Marketplace as we get closer to open enrollment. The notices will tell you your plan’s premium, and if applicable, your after-subsidy premium. Then you can comparison shop during open enrollment to see if a different plan might be a better value.

Out-of-pocket limits are increasing

For 2027 coverage, the maximum allowable out-of-pocket cap is $12,000 – up from $10,600 in 2026.

The Department of Health and Human Services set the $12,000 maximum in January 2026 using a formula set by the ACA. (In the spring of 2026, HHS finalized a rule that would have allowed some Bronze plans to have out-of-pocket limits as high as $15,600. But that was stayed by a court in July, so the highest out-of-pocket limit you’ll see for a single person in 2027 is $12,000.)

  • Who’s affected? The limit on out-of-pocket costs applies to all non-grandfathered (and non-grandmothered) individual and group health plans. Combined, these plans cover more than half of the population. Many plans have out-of-pocket caps that are well below the federal limits, but any individual or group plan can increase its out-of-pocket limit for 2027 as long as it doesn’t go over the federal limits.
  • What can you do? Pay close attention to any communications you get from your health plan, to see if there will be any changes in your deductible and total out-of-pocket exposure for the coming year.

Fewer immigrants will qualify for Marketplace subsidies

Starting with plan year 2027, the only immigrants who qualify for Marketplace subsidies will be:

  • Lawful Permanent Residents (LPR)
  • Cuban-Haitian Entrants (CHE)
  • Compact of Free Association (COFA) migrants.

All other immigrants will no longer qualify for Marketplace subsidies.

  • Who’s affected? Any non-citizens who aren’t in one of the three categories listed above. Immigrants who will no longer qualify for Marketplace subsidies include asylees, refugees, people with Temporary Protected Status (TPS), and people with various types of temporary visas, such as work visas, student visas, U-visas (for victims of certain crimes) and T-visas (for victims of trafficking). An estimated one million people are expected to become uninsured by 2035 as a result of this change.
  • What can you do? If you’re not a U.S. citizen and you currently have subsidized Marketplace coverage, be sure you understand whether your immigration status makes you eligible for ongoing subsidies in 2027. If not, you’ll want to understand how much full-price coverage will cost, and consider whether any of the lower-priced Marketplace plans in your area (a Bronze plan, for example) might be a better fit for your budget.

Oregon will utilize a state-run Marketplace platform

Starting this fall, Oregon residents will use the state-run Explore Health platform to obtain their coverage for 2027, instead of HealthCare.gov. Oregon is the latest state to switch from HealthCare.gov to a state-run Marketplace enrollment platform.

  • Who’s affected? Nearly 106,000 Oregon residents had Marketplace coverage as of early 2026, All of them will transition to Explore Health for 2027 if they wish to keep Marketplace coverage.
  • What can you do? If you’re in Oregon and have Marketplace coverage in 2026, pay close attention to any communications you get from HealthCare.gov and Explore Health (the Oregon Health Insurance Marketplace). Your account should be automatically migrated to the new platform, and you should receive details in early October about how to activate your new account. Window shopping will begin on the new platform on October 15, and open enrollment will begin November 1.

Virginia and Rhode Island introduce state-funded subsidies

For the 2027 plan year, Virginia is joining the list of states that offer state-funded health insurance subsidies in addition to the ACA’s federal subsidies. The Virginia Premium Savings program will be available starting November 1, 2026, when consumers are enrolling in coverage for 2027.

  • Who’s affected? People in Virginia who buy their own health insurance and have household incomes between 138% and 250% of the federal poverty level. For 2027 coverage, that amounts to:
    • Above $22,025 but not more than $39,900 for an individual.
    • Above $45,540 but not more than $82,500 for a family of four.
  • What can you do? If you’re in Virginia and your income makes you eligible for the new Virginia Premium Savings program, the subsidy will be automatically applied to any metal-level plan you select in the Virginia Marketplace. You won’t get the subsidy if you buy coverage outside the Marketplace, or if you buy a Catastrophic plan in the Marketplace.

Rhode Island’s Fiscal Year 2027 budget includes $19 million in state funding to replace some of the federal subsidy enhancements that expired at the end of 2025. But as of late August 2026, Rhode Island’s exchange has not yet clarified how eligibility for the state-funded subsidies will be determined.

HSA contribution limits will increase

As is the case each year, the IRS has indexed health savings account (HSA) contribution limits. If you have HSA-eligible health coverage in 2027, here’s how much you can contribute to an HSA:

  • Up to $4,500 if your HDHP covers just yourself.
  • Up to $9,000 if your HDHP also covers at least one additional family member.

In 2026, the contribution limits were $4,400 and $8,750, respectively.

Note: HSA contributions will lower your household income under the ACA’s rules for how modified adjusted gross income is calculated. This could make you eligible for a larger premium subsidy, or make you eligible for a subsidy when you would otherwise be over the “subsidy cliff.” It’s important to check with a tax advisor for any tax-related questions you might have.

  • Who’s affected? Anyone with an HSA-eligible high-deductible health plan (HDHP) who wants to contribute to an HSA in 2027. As was the case in 2026, all Marketplace Bronze and Catastrophic plans will continue to be HSA-eligible in 2027.
  • What can you do? If you’ll have an HSA-eligible HDHP in 2027, consider whether you’d like to make HSA contributions. You can make the contributions at any point during the year, or even up until the tax filing deadline in April 2028. The money you put into the HSA is pre-tax, and there’s no use-it-or-lose-it rule for HSAs. So if you don’t need to withdraw HSA funds to pay for medical expenses, they will remain in the account (along with any interest, dividends, or investment growth) and you can use the funds to pay medical bills in the future.

Learn more about how HSAs work.

Catastrophic plan eligibility will be further limited

Catastrophic plans are once again available only to people aged 30 or older who obtain a hardship or affordability exemption certificate (and who are in an area where Catastrophic plans are sold).

In September 2025, a Trump administration rule expanded access to Catastrophic plans, making them automatically available in most states to enrollees who didn’t qualify for Marketplace subsidies. That rule was expanded in 2026 to apply nationwide.

But in July 2026, a judge stayed the new rule. That means eligibility for Catastrophic plans is once again limited to the pre-September 2025 rules: a person who is 30 or older must obtain a hardship or affordability exemption certificate to purchase a Catastrophic plan.

Learn more about Catastrophic health plans.


Source link

Who Do We Trust to Decide What Health Care Gets Covered, and at What Price? 


rewrite this content and keep HTML tags

KFF designs, conducts and analyzes original public opinion and survey research on Americans’ attitudes, knowledge, and experiences with the health care system to help amplify the public’s voice in major national debates.


Source link

Protected: Is Prior Authorization a Blessing or a Curse?


rewrite this content and keep HTML tags There is no excerpt because this is a protected post.


Source link

What Do We Get for the Cut Health Insurers Take?


rewrite this content and keep HTML tags

KFF designs, conducts and analyzes original public opinion and survey research on Americans’ attitudes, knowledge, and experiences with the health care system to help amplify the public’s voice in major national debates.


Source link

Are Health Insurers Providing Good Value?


rewrite this content and keep HTML tags

KFF designs, conducts and analyzes original public opinion and survey research on Americans’ attitudes, knowledge, and experiences with the health care system to help amplify the public’s voice in major national debates.


Source link

What’s Driving Rising Health Premiums?


rewrite this content and keep HTML tags

KFF designs, conducts and analyzes original public opinion and survey research on Americans’ attitudes, knowledge, and experiences with the health care system to help amplify the public’s voice in major national debates.


Source link