Home Blog

Exploring Insulin Cost-Sharing Caps for Patients with Private Coverage


rewrite this content and keep HTML tags

Nearly 29 million adults in the U.S. have been diagnosed with diabetes, with 32% of them taking insulin to manage it. The cost of insulin has been a barrier to care for many Americans. A monthly cap on patient cost sharing is one approach aimed at reducing cost-related barriers for people using insulin. While caps do not directly address the underlying price of insulin, they may make patient costs more affordable and support consistent access to this medication. Since 2023, people with Medicare generally have a $35 monthly cap on the cost of insulin. A 2024 KFF poll found that 3 in 4 adults support expanding this cap beyond just those with Medicare. Public support for these protections is also notably bipartisan, with 84% of Democrats and 70% of Republicans in favor.

Applying a cost-sharing cap on insulin to private insurance coverage, including employer coverage, has been gaining momentum among policymakers. Since 2019, an increasing number of state laws have limited cost-sharing for insulin in state-regulated plans, and a federal insulin cost-sharing cap for consumers with private coverage has advanced in Congress this year. This Issue Brief explains the evolution of insulin cost-sharing caps in recent years, including existing state laws and their limitations, the proposed federal legislation, and key policy considerations when assessing whether this approach may improve insulin affordability for consumers.

Background

Insulin affordability has long concerned policymakers. Between 2007 and 2018, the list prices of some forms of insulin increased by more than 260%, according to one study. In Medicare Part D alone, aggregate patient out-of-pocket spending for insulin products quadrupled between 2007 and 2020, according to a KFF analysis.

Examinations have linked high insulin costs, in part, to increasing drug manufacturer list prices and certain contracting and other business practices by pharmacy benefit managers (PBMs). In 2019, the Senate Finance Committee began an investigation into rising insulin prices, culminating in a 2021 report examining the roles of the three major insulin manufacturers (Eli Lilly, Novo Nordisk, and Sanofi) and the major pharmacy benefit managers (CVS Caremark, Express Scripts, and Optum Rx) that administer pharmacy benefits for insurers and employers. The committee concluded that the three drug manufacturers “aggressively” raised the list price of their insulin products, often in lockstep with each other. The “list price” (also called the Wholesale Acquisition Cost (WAC)) is the starting price set by drug manufacturers, later reduced through various discounts and negotiations with PBMs.

The committee also stated that the three largest PBMs have significant marketing power to negotiate rebates with drug manufacturers. Rebates are discounts off the list price that PBMs negotiate with drug manufacturers in exchange for preferred placement of the drug on a health plan formulary. The committee determined that, “… the practice of offering rebates in the insulin therapeutic class appears to be contributing to both increasing insulin WAC prices and limited uptake of lower-priced products.” This, among other factors, the report concluded, can keep insulin out-of-pocket costs high for individual consumers partly because plan formularies often favor higher-cost insulins (with the highest rebates) while excluding or disadvantaging lower-priced insulins.

Other studies have highlighted insulin affordability issues for those who have to pay for it out of pocket at a high list price before meeting their deductible, when insurance begins to pay, as well as those whose cost sharing is pegged to a high list price (e.g., coinsurance). Additionally, privately insured patients typically pay for insulin based on a negotiated rate that does not reflect manufacturer rebates, which may reduce what a plan pays for the insulin but are not necessarily passed through to the patient.

In the years since these evaluations, federal efforts to lower insulin out-of-pocket costs have progressed, notably the passage of the Inflation Reduction Act of 2022 (IRA). Among other prescription drug cost reforms, the IRA established a cost-sharing cap for a month’s supply of any covered insulin for Medicare beneficiaries beginning in 2023. The law limits monthly copayments to the lesser of $35 or 25% of the negotiated price for the insulin in the Medicare Part D plan, or 25% of the price for the insulin negotiated if it is part of the Medicare price negotiation program. A KFF analysis found that out-of-pocket insulin costs for Medicare beneficiaries decreased by half between 2020 and 2024.

Although earlier versions of the IRA would have put the same cap on monthly cost sharing for those in private plans (e.g., employer-sponsored plans and on- and off-Marketplace individual market coverage), this was dropped from the IRA prior to passage. A Peterson-KFF Health System Tracker analysis of 2018 claims data found that a $35 cap would have financially benefited at least 1 in 5 enrollees in private insurance plans who use insulin.

While those with private coverage do not have the cost-sharing protection that Medicare Part D beneficiaries have, Internal Revenue Service (IRS) guidance has allowed those with health savings accounts (HSAs) to access certain preventive services before paying their annual deductible, including insulin and certain supplies (if implemented by their employer or other plan sponsor). Congress added this pre-deductible insulin provision, which is limited only to those with HSAs, in the Inflation Reduction Act. According to the 2026 KFF Employer Health Benefits Survey, 29% of covered workers are enrolled in HSA-qualified high-deductible plans.

Voluntary drug manufacturer price reductions starting in 2023 lower the cost of certain insulins. In March 2023, the three major insulin manufacturers announced that they would significantly cut the list price of certain insulins and expand their existing discount programs for those with private coverage, capping patient cost sharing for insulin at $35 per month at certain retail pharmacies. While the introduction of biosimilar and unbranded insulin also likely played a role in reducing costs, this voluntary manufacturer price reduction has largely been attributed to a change in how Medicaid rebates are calculated. Under the Medicaid Drug Rebate program, drug manufacturers give rebates to federal and state governments in exchange for coverage of their drug under the Medicaid program. The amount to be paid in rebates was limited under a formula in place since 2010. The American Rescue Plan Act of 2021 eliminated the limit on these rebates to Medicaid. This would have substantially increased what drug manufacturers pay to Medicaid in rebates for certain insulins if drug manufacturers did not reduce the price of insulin available to commercial payors.

Other federal action and state litigation aim to address insulin prices and costs. While congressional actions focused on reducing costs for prescription drugs broadly—including a PBM transparency and rebate reform law passed earlier this year and efforts to bring more lower-cost biosimilars to market—likely impact insulin costs, other activity focused specifically on insulin pricing includes:

Federal Trade Commission (FTC) action. The FTC filed an administrative complaint in September 2024 against the three largest PBMs (and their subsidiaries) alleging that they systematically prefer high-list-price insulin products with high rebates over lower-priced ones. According to the FTC, these PBMs artificially inflated prices, shifting costs to consumers and constituting an unfair act or practice and unfair method of competition under federal law. In 2026, the FTC settled with two of these PBMs (Express Scripts and CVS Caremark), which agreed to make specific changes to their prescription drug pricing and rebate practices by 2028, including providing broader access to existing PBM programs that cap enrollee out-of-pocket payments for insulin at a set dollar level, some as low as $25 for a month’s supply. PBMs also agreed to count cash payments made for medications using TrumpRx coupons toward a patient’s deductible and out-of-pocket maximum if certain legal and regulatory changes are made. It is not clear whether and how this will be implemented.

Separate state litigation. Some state attorneys general (AGs), cities, school districts, and other plaintiffs have sued the leading insulin manufacturers and PBMs, alleging anticompetitive and/or deceptive practices related to high insulin prices. State AGs in Republican-led and Democratic-led states have filed actions over the past three years, many of which have been consolidated with hundreds of other similar cases in a federal district court. These cases largely allege violations of state antitrust and consumer protection laws, seeking both to stop drug manufacturer and PBM practices that they allege inflate insulin prices, and to secure damages for affected consumers and employers. No major court decisions or settlement agreements have been issued yet in these cases.

Alternative pathways to lower-cost insulin are gaining momentum. New approaches to insulin production and distribution are opening new access points for patients. For instance, California recently began producing its own biosimilar insulin (glargine) through its CalRx program, allowing patients who use this specific type of insulin to purchase it at a lower cost, with or without insurance. PBMs and other third parties are also manufacturing private-label biosimilar insulins, but their long-term impacts on patient costs are unclear: with financial incentives to promote their own private-label drugs, PBMs are not inherently incentivized to pass on savings to insurers and their enrollees.

A growing direct-to-consumer sales market gives patients another avenue to purchase insulin at discounted prices, mostly on a cash-pay basis outside of insurance, from online pharmacies such as Amazon Pharmacy and certain drug manufacturers. Additionally, discount platforms like GoodRx and TrumpRx provide coupons that consumers can use to purchase medications from participating pharmacies. Certain consumers, such as those with low incomes, may find even lower costs from manufacturer-sponsored patient assistance programs and through other pathways.

State Insulin Cost-Sharing Caps

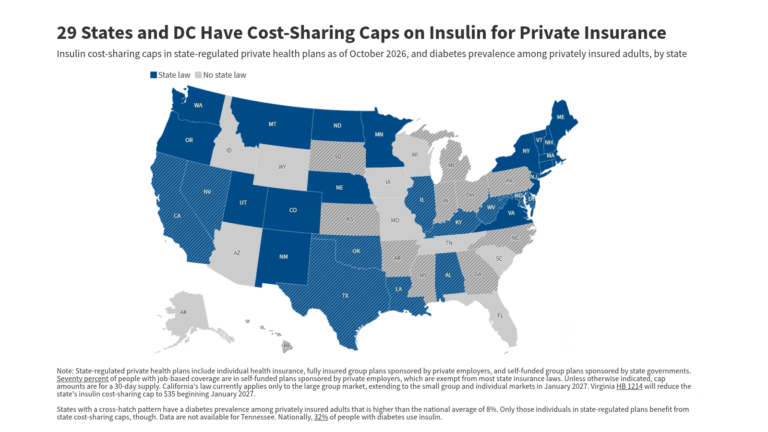
According to KFF analysis of state laws, as of October 2026, 29 states (nearly 60%) and the District of Columbia have enacted laws that cap cost sharing for insulin for privately insured patients, beginning with Colorado in 2019 (Figure 1). At least 11 states with relatively high rates of diabetes do not have laws capping insulin cost sharing. While state cost-sharing protections can provide a useful framework for developing federal policy, as discussed below, their reach is limited to a relatively small share of people with private health coverage. Separately, some states have eliminated cost sharing for insulin in certain types of ACA Marketplace plans and/or have implemented other programs to help uninsured and underinsured patients afford their insulin.

Cost-sharing Caps for Those with Private Insurance

Dollar Cap Amounts

The dollar amounts of insulin cost-sharing caps vary by state. While some states have lowered their caps since enacting their first laws, caps currently range from $0 in New York and Massachusetts (generic only) to $100 in Alabama, Colorado, Delaware, and Vermont for a 30-day supply (Figure 1). The most common cap amount for a 30-day supply is $35. About three-quarters of states with insulin cost-sharing caps currently limit out-of-pocket spending to $35 or less, while seven states have caps higher than $35. (One of these states, VA, will reduce its cost-sharing cap to $35 beginning January 2027.) Two states (OK and OR) also extend corresponding out-of-pocket caps for a 90-day supply of insulin. Links to current state laws are included in the map below.

Dollar Cap Structure

The structure of insulin cost-sharing caps is relevant for people who use multiple insulins each month. While caps in most states are structured as a separate amount for each prescription, at least four states (CO, DE, VT, and WV) currently have aggregate caps that apply to total out-of-pocket spending for all covered insulin products a patient may purchase in a month. (VA’s cap will change from separate to aggregate in 2027.) For example, under a $35 aggregate cost-sharing cap, a patient who uses two different types of insulin would pay no more than $35 per month, compared to no more than $70 per month under a separate per-prescription cap.

Drugs and Other Items Covered by Caps

Many state caps apply broadly to prescription drugs containing insulin used to treat diabetes, regardless of form (e.g., vial, pen, inhaled) or type (e.g., rapid-acting, short-acting, intermediate-acting, long-acting). Some states have additional requirements. For example, Connecticut’s cost-sharing cap also applies to noninsulin diabetes drugs (e.g., glucagon). Most caps apply only to the actual drug product itself, but five states (CT, DE, MN, ND, and WV) and DC also have separate out-of-pocket caps for diabetes-related medical supplies and equipment such as glucometers, testing strips, pens and syringes, and laboratory testing for diabetes-related markers, ranging from $25 (ND) to $100 (WV and DC) per monthly supply of covered items. (VA will institute a $35 cost-sharing cap for supplies beginning in 2027.)

Limitations of State Caps

According to KFF analysis of the 2024 Behavioral Risk Factor Surveillance System (BRFSS) data, 8% of privately insured adults have been diagnosed with diabetes, ranging from 4% in the District of Columbia to 12% in West Virginia (Figure 1). Although state cost-sharing caps generally apply to both the individual and group markets, in practice, only a small fraction of those individuals benefit from these laws. A key limitation of state insurance laws is that they generally don’t apply to most people with employer-sponsored coverage, the largest source of coverage for those under age 65. Federal law (the Employee Retirement Income Security Act of 1974, or ERISA) exempts self-funded health plans established by private employers (but not public employers) from most state insurance laws. In 2026, 7 in 10 (70%) workers with job-based coverage are enrolled in this type of plan. Put into perspective, this means only 3 in 10 (30%) workers with employer-sponsored insurance, plus the much smaller share of people with state-regulated individual coverage, such as ACA Marketplace plans, are reached by state cost-sharing caps. Absent a federal cost-sharing cap, which would extend to plans governed by ERISA, the scope and application of state cost-sharing protections will remain limited.
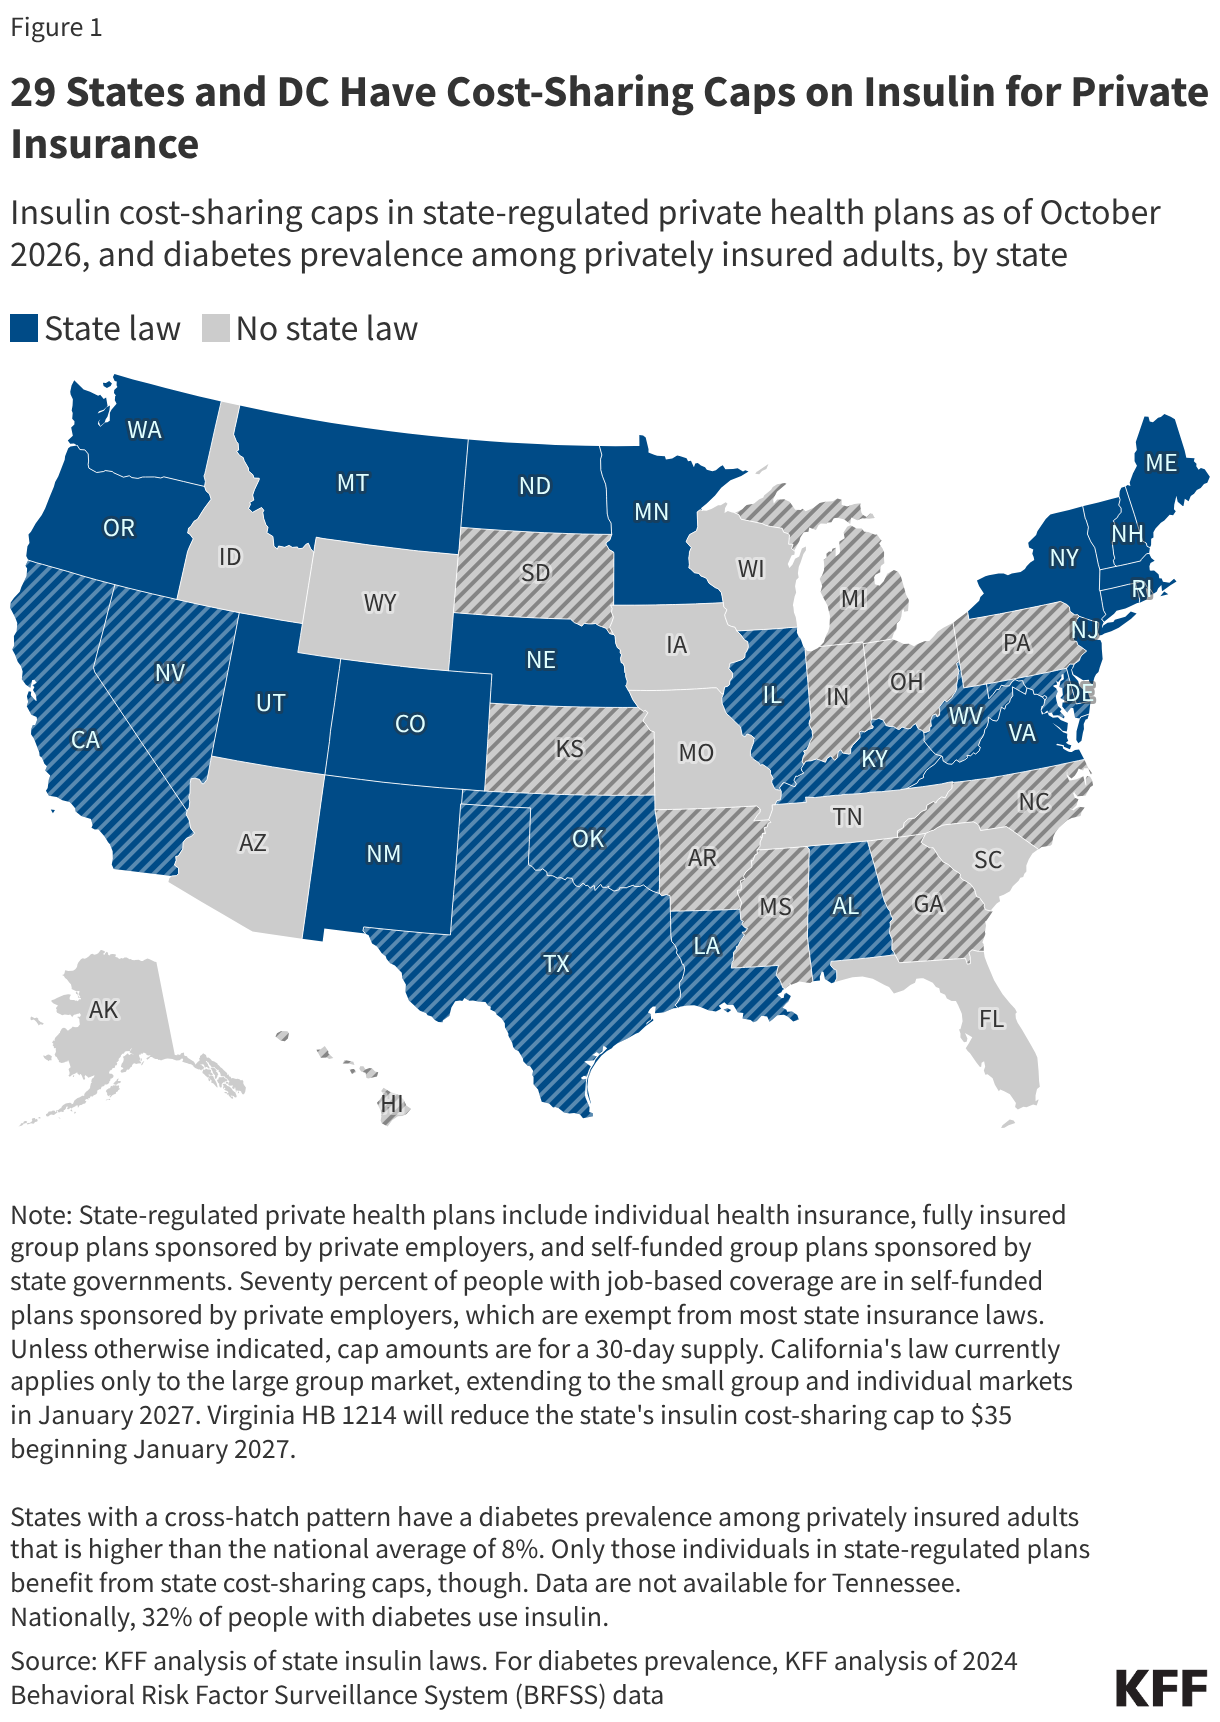
29 States and DC Have Cost-Sharing Caps on Insulin for Private Insurance (Choropleth map)

No Cost Sharing for Insulin in Some State ACA Marketplace Plans

In addition to the broadly applicable statutory cost-sharing caps described above, at least three state-based ACA Marketplaces have used their administrative authority to eliminate all cost sharing for specific chronic condition maintenance drugs, including insulin, for certain enrollees. For example, enrollees in specific Marketplace plan types or cost-sharing tiers in the District of Columbia and Maryland have $0 cost sharing for select insulins (and certain related supplies). Cost sharing was also eliminated for lower-income Marketplace enrollees in Massachusetts.

Out-of-pocket Insulin Caps for the Uninsured and Underinsured

According to KFF’s analysis of 2024 BRFSS data, 7% of uninsured adults have been diagnosed with diabetes. Uninsured individuals generally receive less health care than those with insurance. In 2024, 42% of uninsured adults under age 65 with diabetes delayed or avoided receiving needed care due to the cost, compared to 11% of those with insurance. At least three states—CO, ME (until 2027), and MN—have implemented separate affordability programs that cap insulin costs for uninsured, as well as certain underinsured patients.

Affordability Safety Net Programs

Laws in Minnesota and Maine require large insulin manufacturers to establish insulin patient assistance programs for uninsured and underinsured residents of those states with family income of 400% or less of the federal poverty level. Under these “continuing needs” programs, eligible patients receive a 90-day supply of insulin at no charge from the manufacturer for up to a year, though pharmacies may charge the patient a dispensing fee of up to $50 per fill. Colorado also has a continuing-needs insulin program for uninsured and underinsured individuals, but with some differences, including that eligibility is not limited to those with lower incomes and the optional dispensing fee is based on a 30-day supply.

Urgent Need Programs

Minnesota, Maine (until 2027), and Colorado require insulin manufacturers to establish “emergency” insulin programs that provide one 30-day supply of insulin per year to eligible uninsured and underinsured residents who have less than a 7-day supply of insulin readily available. While there is no charge for the insulin itself, pharmacies are permitted to charge the patient a dispensing fee of up to $35.

Proposed Federal Insulin Cost-Sharing Cap

Bipartisan federal legislation known as the Improving Needed Safeguards for Users of Lifesaving Insulin Now (INSULIN) Act of 2026 would impose a national insulin cost-sharing cap for private insurance and establish a pilot program to assist the uninsured. Similar bills have been introduced in previous years, but this year’s was considered and approved by the Senate Health, Education, Labor and Pensions (HELP) Committee over the summer; a companion bill was subsequently introduced in the House. Whether Congress will try to advance this legislation in the remaining lame-duck session this year or start over with the new Congress next year is unknown. Key provisions of the INSULIN Act include:

A requirement for private plans to cover “selected insulin products.” Plans would be required to cover at least one insulin of each dosage form of each insulin type. Plans and insurers make the selection, so coverage of specific insulins would likely differ by plan. The requirement extends to all employer-sponsored health plans (insured and self-funded), including non-Federal governmental plans, as well as individual market plans (including Marketplace plans). The legislation does not apply to non-insulin diabetes medications or supplies.

A $35 cost-sharing cap for a 30-day supply of insulin across all private insurance coverage. The INSULIN Act would require plans to cap enrollee cost-sharing payments for the plan’s selected insulin products at $35 per 30-day supply, or 25% of the plan’s negotiated price, whichever is less. Plans are not required to apply this cap for insulins delivered by an out-of-network provider. While the legislation does not define “negotiated price,” it requires that the negotiated price is “net of all price concessions received by or on behalf of the plan or issuer,” including PBMs and third-party administrators. This likely means that the negotiated price must take into account all rebates received by these entities.

No deductibles would apply before cost sharing starts. Health plans would be prohibited from applying a deductible to their selected insulins. This would apply even to catastrophic plans available on ACA Marketplaces where, currently, enrollees must pay a high deductible ($10,600 for an individual or $21,200 for a family in 2026) before their coverage kicks in. The exemption from the deductible for the selected insulins cannot be treated as increasing the actuarial value of a qualified health plan.

Selected insulin would be treated as an essential health benefit. The legislation also states that the selected insulin product should be treated “as though such benefits were required to be provided” as an essential health benefit (EHB). Insurers in the individual and small group market are required to cover EHBs and count patient cost sharing for them toward the ACA’s required patient out-of-pocket maximum ($10,600 for an individual or $21,200 for a family in 2026).

Limits on prior authorization for selected insulins. The legislation would prohibit plans and insurers from imposing prior authorization requirements on the selected insulin products except as “clinically justified for safety reasons, to ensure reasonable quantity limits and as specified by the Secretary.” While this does not ban prior authorization, it might put new requirements on plans to justify why prior authorization is required for the plan’s selected insulins.

New pilot program for the uninsured. The bill would also create a temporary program to help address barriers for uninsured people using insulin. The 5-year, $100 million pilot program would be implemented across 10 states with high rates of uninsured people with diabetes. States would direct grant funds to assist in obtaining insulin and expanding access to on-site pharmacies at federally qualified health centers, provide additional support to community pharmacies where uninsured individuals obtain low-cost insulin, and assist low-income patients in accessing manufacturer drug discounts on insulin. The bill would also establish a separate $2 million national insulin resource center and hotline project to connect patients with outreach and assistance programs.

Changes to increase access to biosimilars. The INSULIN Act also proposes changes to Food and Drug Administration (FDA) approval processes to provide quicker access to new biosimilar medications. The FDA has approved a total of six insulin biosimilars since it implemented a new regulatory pathway to approval for biologic drugs in 2020.

Policy Considerations

Expanding out-of-pocket caps at the state level, or passing a federal out-of-pocket cap for insulin, could make insulin more affordable for consumers and provide some assurance that their out-of-pocket costs for insulin should not exceed a certain threshold. While the INSULIN Act of 2026 would fill the gaps in the current patchwork of state insulin cost-sharing caps and provide a federal floor of protections, it does not regulate the price of insulin or directly address the current dynamics of manufacturer rebates and formulary placement that may have led to high prices. Some considerations for policymakers include:

The extent to which a federal cap would substantially change what patients with private coverage pay for insulin. In recent years, some studies of state out-of-pocket caps on insulin showed only modest reductions in consumer out-of-pocket costs, possibly because many with private insurance already had relatively low cost sharing for some insulin types. A Department of Health and Human Services (HHS) analysis estimated that average out-of-pocket spending for a monthly supply of insulin was under $20 in 2025, which it attributed to a range of factors including manufacturer list price reductions and patient assistance programs, state cost-sharing caps, biosimilar competition, and pre-deductible coverage of insulin for those with health savings accounts. However, another recent analysis found that even though the share of insulin users with employer-sponsored coverage who spent over $35 out of pocket for a 30-day supply decreased from 2019 to 2023, about four in ten (41%) still spent over $35 per month in 2023, including more than two in ten (23%) who spent more than $50 per month. Although the 2023 claims data predate some of the more recent voluntary manufacturer price reductions and state-level insulin cost-sharing caps, some of these individuals could likely still benefit from the proposed federal cost-sharing cap.

Although direct-to-consumer (DTC) options offered by some manufacturers and online pharmacies may provide some insulin users with a less expensive alternative than the proposed $35 cost-sharing cap, federal law does not currently require cash payments made through these channels to count toward a private health plan’s deductible or out-of-pocket maximum. The INSULIN Act would not change this. Furthermore, it remains to be seen whether manufacturer-sponsored DTC options are an attempt to foreclose additional state and federal cost-sharing caps or whether they could affect the durability of voluntary price reductions.

How other federal actions could intersect with the proposed cost-sharing cap and impact insulin prices for privately insured and uninsured consumers. The inclusion of insulin on the Medicare drug price negotiation list, another federal law that will require PBMs to pass through all rebates to health plans sponsored by private employers, and new requirements on PBMs under FTC settlements are just some of the moving parts that could influence insulin pricing going forward. This shifting policy landscape operates alongside an evolving supply-side landscape. Beyond the scope of this issue brief are equally complex dynamics in FDA approval, manufacturing, and patient use of biosimilars and unbranded insulin, such as those developed under California’s new public program and by PBMs.

The impact of an out-of-pocket insulin cap on enrollees’ private insurance premiums and other out-of-pocket costs. Although the Congressional Budget Office (CBO) has not released a cost estimate for the INSULIN Act of 2026, insurers and employers could face increased plan costs, which they could pass on to enrollees through higher monthly premiums. In addition, to the extent that a federal insulin cost-sharing cap shifts more plan sponsor spending toward insulin, enrollees could see higher cost sharing for other items and services if plans seek to maintain their overall actuarial value (the average share of health care expenses for covered services that are paid by the plan, as opposed to those paid out-of-pocket by the enrollee). These dynamics could increase the overall financial burden on all consumers, including those taking other high-cost medications for diabetes (e.g., GLP-1s), cancer, or other illnesses that lack out-of-pocket caps.
Source link

How Does Medical Inflation Compare to Inflation in the Rest of the Economy?


rewrite this content and keep HTML tags

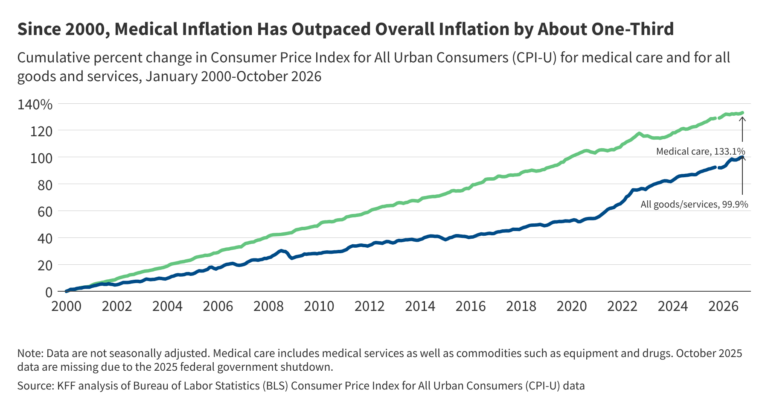
Medical care prices and overall health spending historically outpace growth in the rest of the economy. Health costs represent a growing share of gross domestic product, and many American families have seen the costs of health services and health insurance premiums grow faster than their wages. Between January 2000 and October 2026, medical care prices grew 33% more than overall consumer prices, with the price of hospital services experiencing the fastest growth.

This KFF analysis describes both short-term and long-term inflation trends to provide a more nuanced understanding of how healthcare price growth compares to price growth in the rest of the economy.

The analysis primarily examines inflation in prices by urban consumers using Consumer Price Index for All Urban Consumers (CPI-U) data from the Bureau of Labor Statistics (BLS). This analysis and others can be found on the Peterson-KFF Health System Tracker, an information hub dedicated to monitoring and assessing the performance of the U.S. health system.


Source link

Second-Year Rural Health Fund Awards Per Rural Resident Continue to Vary Widely


rewrite this content and keep HTML tags

On November 9, 2026, the Centers for Medicare & Medicaid Services (CMS) announced second-year state awards from the $50 billion Rural Health Transformation Program (referred to here as the “rural health fund”). The rural health fund was created as part of the July 2025 budget reconciliation law, once known as the “One Big Beautiful Bill,” to help offset the impact of the law on rural areas. In particular, it was projected that the law would reduce federal Medicaid spending by $911 billion over ten years (based on estimates released shortly after enactment), including by an estimated $137 billion in rural areas, according to KFF analysis.

CMS awarded $10 billion in state grants through the rural health fund for fiscal year 2027. CMS did the same for fiscal year 2026 and will continue to do so from fiscal years 2028 through 2030, for a total of $50 billion over five-year period. States had a one-time opportunity to apply for funding, and all states were approved, meaning that they are eligible for funding for all five years of the program, barring any decision by CMS to reduce or eliminate their award.

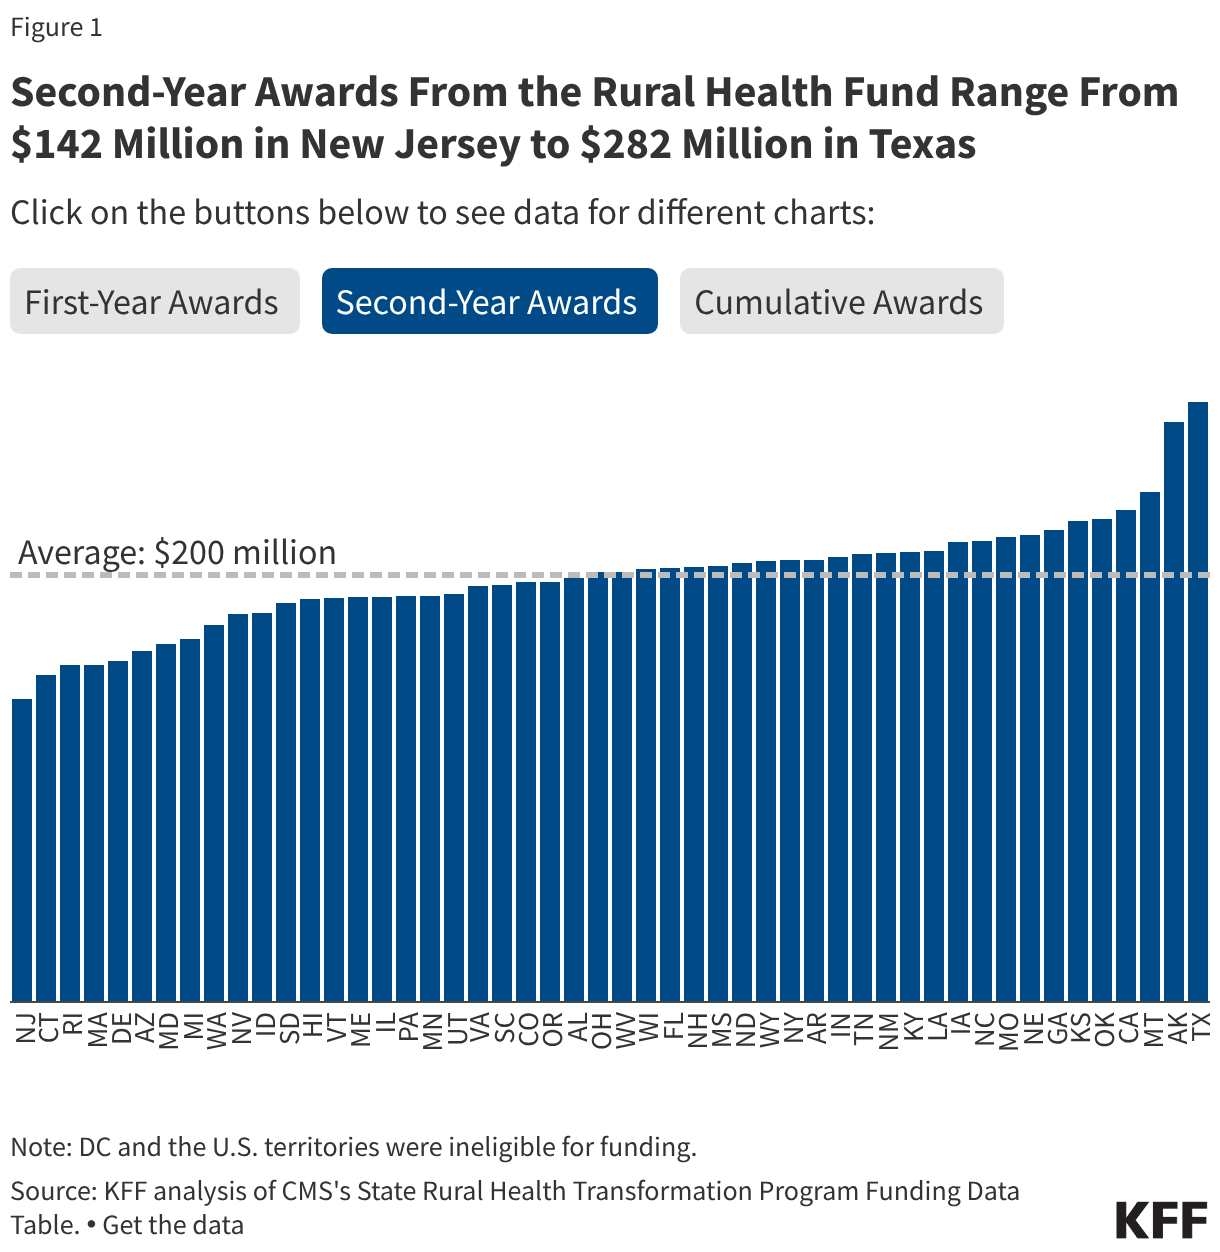
State awards for fiscal year 2027, the second of five years, average $200 million, ranging from $142 million in New Jersey to $282 million in Texas (Figure 1). Differences in total awards across states in the second year are modest relative to large differences in rural populations and rural health needs more generally (as was the case in the first year of the program and will likely be true in future years). For example, Texas has about thirty times as many rural residents as New Jersey (4.3 million versus about 140,000) but is only receiving about twice as much funding in the second year ($282 million versus $142 million). Differences in total awards across states are relatively modest primarily because half of the rural health fund (50%) is being distributed equally across approved states, regardless of need, as required by law. Because all states have been approved for funding, each is slated to receive $100 million from this half of the fund in each of the five award years.

Texas, Alaska and Montana are receiving the largest total awards in the second year. While Texas has the largest rural population in the country, Alaska and Montana have the fifth- and fifteenth-smallest rural populations, respectively. Alaska and Montana likely received relatively large awards at least in part because a portion of the fund was distributed to the five largest states based on land area. New Jersey, Connecticut, and Rhode Island are receiving the smallest awards in the second year. These are all states with relatively small rural populations.

Second-Year Awards From the Rural Health Fund Range From 2 Million in New Jersey to 2 Million in Texas (Column Chart)

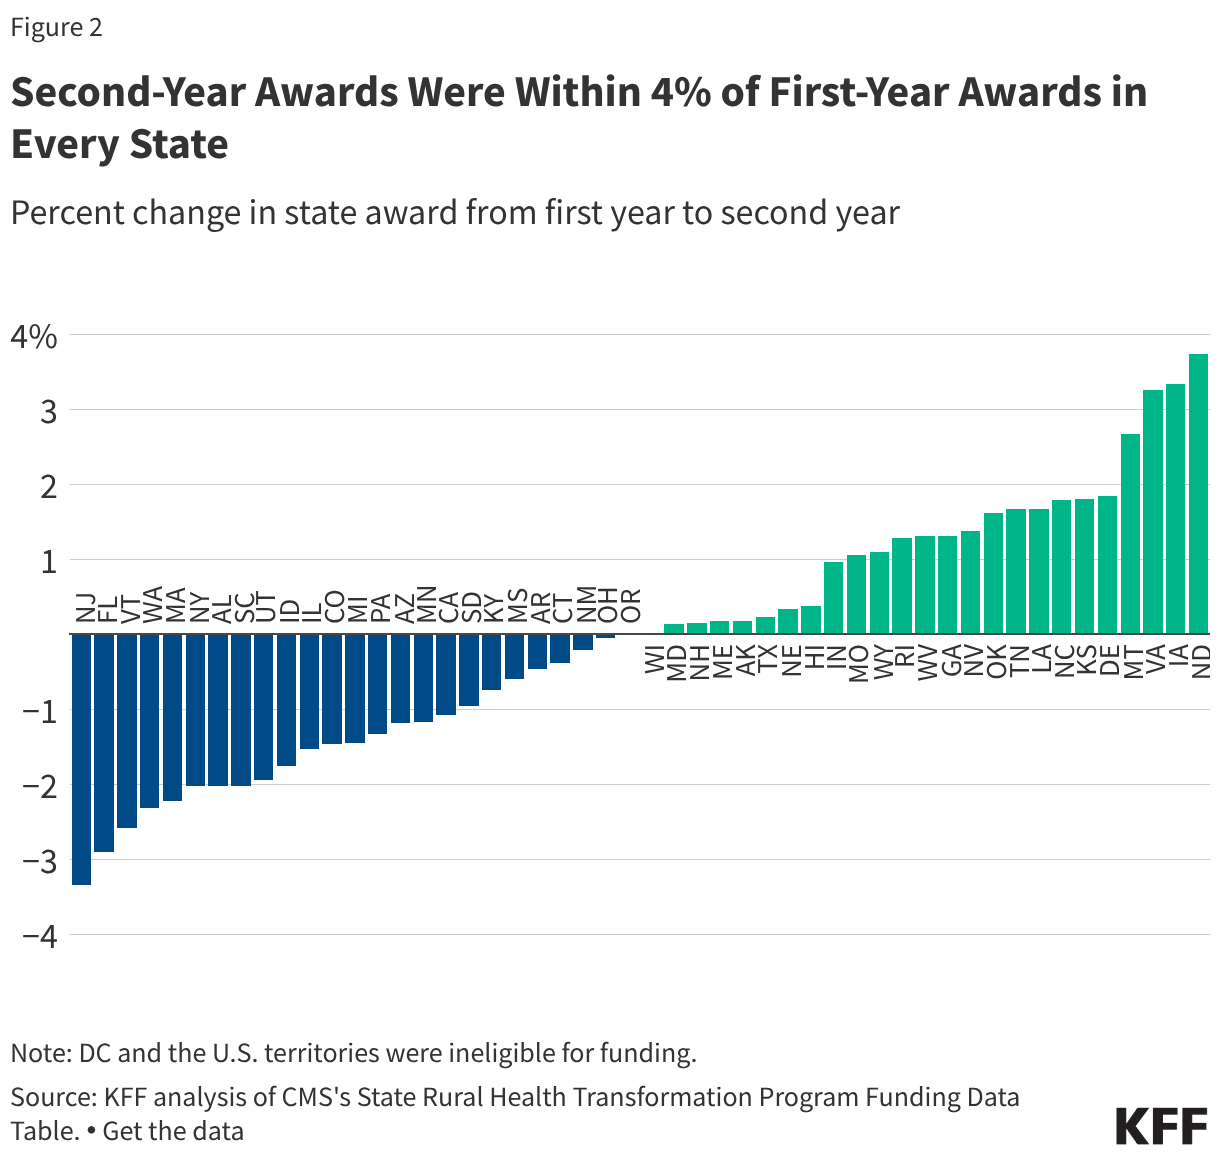
Second-year awards were within 4% of first-year awards in every state (Figure 2). First and second-year awards were likely similar because most of the rural health fund (75%) is locked in place, barring any decision by CMS to reduce or eliminate the award for a given state. In particular, CMS is required by law to distribute half (50%) of the funding equally across approved states (all 50 states), and the agency is distributing a quarter (25%) of the funding based on measures of state need, calculated once and used for the life of the program. Based on CMS guidance, the remaining quarter (25%) is being distributed based on state initiatives, state policy, and other factors. The distribution of those dollars could change over time, e.g., based on a state’s progress in implementing their initiatives and enacting policies committed to in their applications.

Second-Year Awards Were Within 4% of First-Year Awards in Every State (Column Chart)

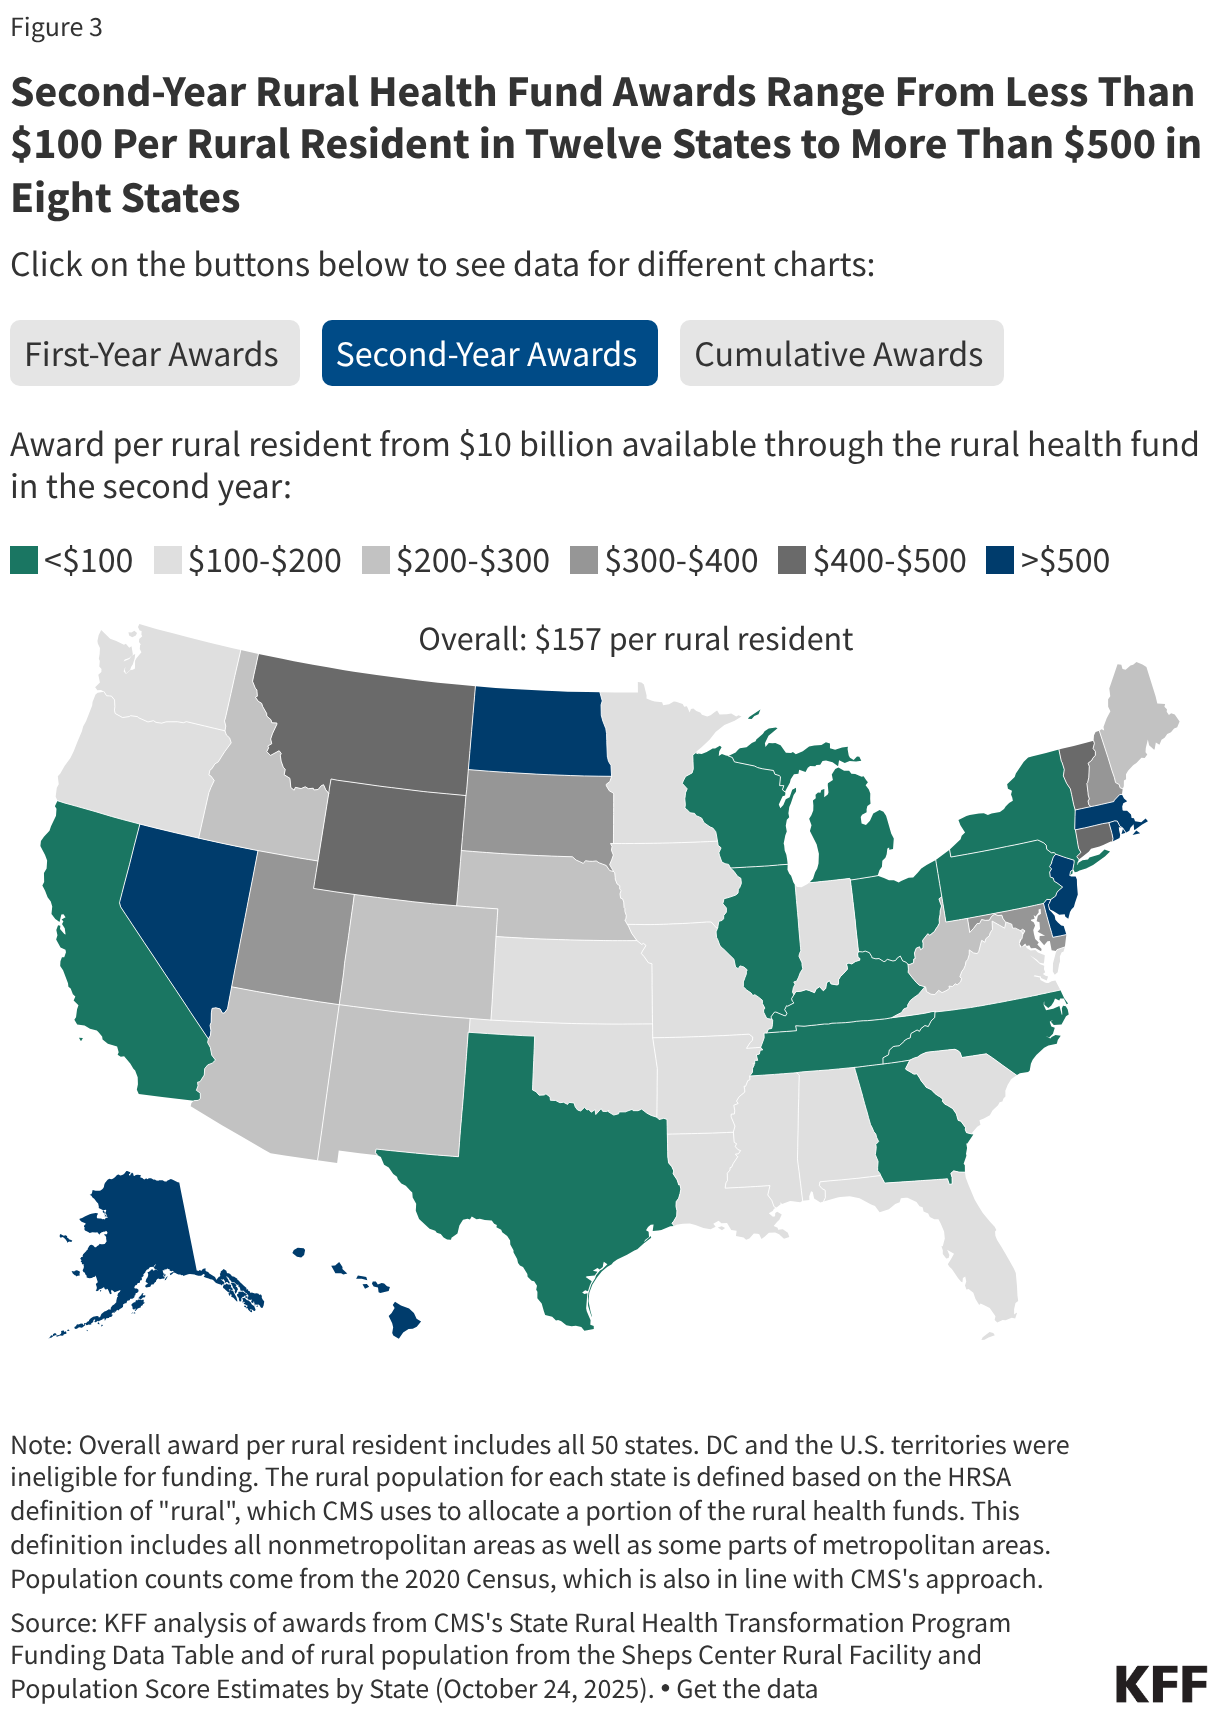
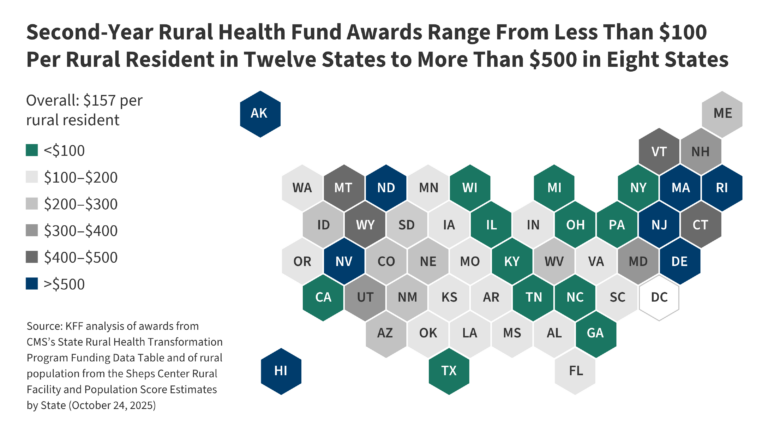
Second-year awards per rural resident vary widely across states, ranging from less than $100 in twelve states to more than $500 in eight states (see Figure 3). State awards are partially, but not closely, tied to rural population, meaning that second-year awards per rural resident are generally relatively small among states with the largest rural populations. For example, Texas has the largest rural population in the country—and the largest total award in the second year—but will receive the smallest payment per rural resident (about $70 in 2026). In contrast, states like Rhode Island, New Jersey, and Alaska, with far fewer rural residents, will receive substantially higher amounts per rural resident (about $6,390, $1,030, and $990 respectively, with Rhode Island being an extreme outlier). Only a quarter of the $50 billion fund is being distributed exclusively based on measures of state need, with just 5% of the fund that is based on rural population.  Other measures of need, according to CMS, include the number of rural facilities, land area, the share of hospitals receiving Medicaid disproportionate share hospital (DSH) payments, and other factors.

Second-Year Rural Health Fund Awards Range From Less Than 0 Per Rural Resident in Twelve States to More Than 0 in Eight States (Choropleth map)

It remains to be seen how states will distribute their awards across various activities and entities. State annual and quarterly progress reports to CMS will include standardized information about how much money various entities are receiving from states and for what purposes. A full accounting of first-year obligations to direct recipients will not be available until states submit their first quarterly reports, due November 29, 2026, and the same details about the second round of state awards will not be available until late 2027. While CMS has stated they will release state progress reports to the public upon request, it does not plan to do so proactively. Annual progress reports are available for several, but not all, states from KFF Health News. CMS has released some information about how states are using and obligating funds (such as a summary of the states’ first annual progress reports), and approved plans and budgets are available for most states from KFF Health News. However, unlike the state progress reports, these sources do not reveal how much money is distributed across various entities and how those entities are using the funding.

This work was supported in part by Arnold Ventures. KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities.


Source link

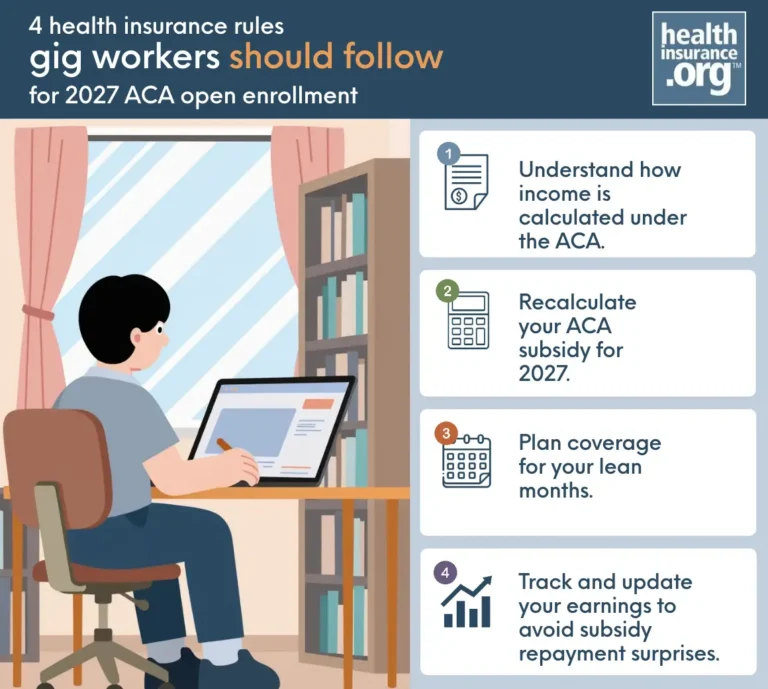
Four rules gig workers should follow when choosing 2027 health insurance


rewrite this content and keep HTML tags

Key takeaways

  • Calculate your income correctly. Marketplace subsidies are based on household income, including net earnings from gig work.
  • Recheck your 2027 subsidy. Your financial assistance and net premium may change, even if you keep the same plan.
  • Choose coverage you can afford year-round. Consider premiums during slow months and what you could pay when you need care.
  • Track your income and update the Marketplace. Reporting significant changes can help you avoid unexpected subsidy repayments.

If you’re a gig worker, choosing the wrong Marketplace health plan or miscalculating your income could cost you thousands of dollars in unexpected medical expenses or premium tax credit repayments. And because gig worker earnings may fluctuate throughout the year, finding affordable coverage can be especially challenging.

Whether you’re a rideshare driver, freelancer, or other independent contractor, following these four rules can help you choose the right coverage for 2027, manage your costs, and avoid expensive surprises.

Rule 1: Understand how household income is calculated under the ACA and what that means for gig workers

The ACA has its own version of modified adjusted gross income (MAGI), which is used to determine eligibility for expanded Medicaid and for Marketplace subsidies.

For many people, this version of MAGI ends up being the same as their adjusted gross income (AGI) that shows up on their tax return, but there are a few amounts that have to be added to AGI if you have them. So your ACA MAGI might be more than your AGI, but it won’t be less.

  • Deductions and adjustments that are “above the line” on your tax return (taken before AGI is calculated) will reduce your MAGI.
  • Deductions taken “below the line” (after AGI is calculated) will not reduce your MAGI.

Modified adjusted gross income (MAGI) calculatorTool

A few points to keep in mind for gig workers calculating their MAGI:

  • When you choose a Marketplace plan during open enrollment, you’ll be projecting your total income for the coming year. So although your AGI from the previous year’s tax return can be a helpful starting place, you might not earn the same amount in the coming year. (As discussed in more detail below, you’ll reconcile everything with the IRS after the year is over and your actual income is known.)
  • As is the case for anyone buying health insurance in the Marketplace, subsidy eligibility depends on total household MAGI, and married couples must file joint tax returns to qualify for Marketplace subsidies. So make sure you’re including all household income – not just your gig work income. And if you have multiple gigs, you need to include the income from all of them.
  • But don’t forget to subtract your eligible business expenses (that you’ll deduct on your tax return) when you’re projecting your household income. Itemized and standard deductions do not reduce ACA MAGI, since they’re taken after AGI on your tax return. But gig workers’ eligible business expenses are subtracted “above the line,” so they do reduce ACA MAGI.
  • The “no tax on tips” rule – in effect from 2025 through 2028 – allows many gig workers to avoid paying income tax on tips. But this is calculated after AGI on your tax return. So the tip income is still included in your ACA-specific MAGI.
  • If you contribute to a health savings account (HSA) or make deductible contributions to an eligible retirement account like an IRA, those contributions can reduce your income when ACA MAGI is determined.
    Note: You must have an HSA-eligible high-deductible health plan to contribute to an HSA. All Bronze Marketplace plans are HSA-eligible starting in 2026. Catastrophic Marketplace plans are also HSA-eligible, but premium subsidies cannot be used to purchase them.
  • Gig workers can deduct their health insurance premiums using the self-employed health insurance deduction, which is another “above-the-line” deduction that reduces AGI and thus reduces ACA MAGI.
    Note: You can only deduct the portion that you pay yourself, and that might change when the year is over and you’re reconciling your subsidy on your tax return.

Learn more in our guide to self-employed health insurance, and our guide to health insurance for gig workers.

Simplified example:

Bob works as a rideshare driver, and also delivers food on the weekends to supplement his income. Here’s what he’s projecting for the coming year:

  • Bob expects to earn $37,000 between the two gigs, not including tips.
  • Bob expects his tips to be about $4,500, bringing his total income to $41,500.
  • Bob thinks his deductible business expenses will be $16,000, leaving a net business income of $25,500.
  • Bob plans to contribute $1,000 to an HSA and $1,500 to a traditional IRA. This brings his ACA MAGI to $23,000, making him eligible for significant Marketplace subsidies.

Rule 2: Recalculate your ACA subsidy eligibility for 2027

If you already have Marketplace coverage in 2026, don’t assume that your subsidy and net premium will stay the same for 2027. These amounts change each year, and you don’t want to be caught off guard by a new net premium in January.

This is especially important when enrolling in 2027 coverage because health insurers are changing their premiums, and some are exiting Marketplace markets altogether. Those changes can affect both the subsidies available to you and the amount you’ll pay for coverage. Even if your income hasn’t changed, the plan that was most affordable for you in 2026 might not be your best option for 2027.

2027 ACA open enrollment: What’s changingArticle

Federal subsidy enhancements expired at the end of 2025. This resulted in significantly higher average net premiums in 2026 and many people downgrading to Bronze plans, even though most Marketplace enrollees still qualify for subsidies.

For 2027, overall affordability for subsidized enrollees will remain roughly the same as 2026, but you might need to switch to a different plan to avoid a premium increase. Your net premium for 2027 will depend on the cost of the plan you choose as well as the amount of your subsidy. So the factors that will affect your net premium include:

  • The number of people who will be on your 2027 tax return
  • The ages of everyone applying for coverage
  • The household income you project for 2027
  • The cost of the benchmark plan (for yourself and any family members enrolling with you)
  • The cost of the plan you choose

Letting your plan auto-renew is not in your best interest, even if that plan served you well in 2026 and is available for renewal. It’s better to actively comparison shop during open enrollment. And it’s also important to make sure your income projection for 2027 is as accurate as possible, to avoid the unwelcome surprise of potentially having to repay excess premium subsidies when you file your 2027 tax return.

Subsidy calculatorTool

Rule 3: Choose coverage you can afford during your lean months

Your health insurance premiums have to be paid every month to keep your coverage in force. For gig workers, freelancers, and other independent contractors, income can vary significantly throughout the year, making it difficult to budget for fixed expenses like health insurance.

If your projected income for the whole year is changing, you can update your Marketplace account and get your subsidy adjusted mid-year (more about that below). But otherwise, you need to make sure that you’ll be able to afford your premiums every month of the year, including your slowest months when your income is lower than normal.

That could lead you to pick the plan with the cheapest premium, but you also need to consider out-of-pocket costs (deductible, copays, and coinsurance). Unlike premiums, you only pay out-of-pocket costs if and when you receive medical care. But depending on the plan you select, your out-of-pocket exposure for covered, in-network care could be as high as $12,000 for a single person in 2027.

Other factors being equal (like provider networks, for example), plans with higher out-of-pocket costs will tend to have lower premiums. But you should consider both – as well as provider networks and covered drug lists – when you’re picking a plan. You need to be able to afford your premium all 12 months of the year in order to keep your coverage. But you also have to be able to afford the out-of-pocket costs if you end up needing medical care during the year.

So you might find that a plan with a higher – but still manageable – monthly premium will provide more benefits if and when you need care.

How can I choose the best health insurance for me?Article

Rule 4: Monitor your income throughout the year to avoid subsidy repayment surprises

The ACA’s premium subsidies are a tax credit. But unlike tax credits that can only be claimed after the year is over and you’re filing your taxes, the ACA allows people to take their premium tax credits up front, as an advance premium tax credit (APTC).

So instead of having to pay the full premium all year and then recouping the premium tax credit at tax time (which is still an option), most Marketplace enrollees choose to have their premium tax credit sent directly to their health plan each month, reducing the amount they have to pay themselves.

When you’re enrolling in the fall of 2026 for a plan that will cover you in 2027, you’re projecting how much you think you’ll earn in 2027, and your upfront subsidy is based on that projection.

But then you have to reconcile your APTC once the year is over: If your subsidy should have been larger, the IRS will give you the difference when you file your tax return (as an addition to your refund, or subtracted from what you owe). But if your APTC was too big, you’ll have to repay some or all of it when you file your taxes.

You will have to repay excess ACA subsidies. Starting with the 2026 tax year, there’s no longer a repayment cap for excess advance premium tax credits. If your income is higher than projected and you receive more financial assistance than you’re eligible for, you will have to repay the entire excess amount when you file your taxes.

Update your Marketplace application when your projected annual income changes significantly.

Projecting income for the coming year can be particularly challenging if you’re a gig worker or freelancer, since it can be hard to know how steady your gigs will be, whether you’ll gain or lose clients, or other factors that might affect your earnings. And although you might plan to make contributions to an HSA or retirement account and factor that into your total income projection, other expenses might come up during the year that keep you from making those contributions.

Whatever the reason, you might find that as the year goes on, you can tell that your income is on track to be different from what you projected. If it’s only slightly different, you might decide to just sort it out at tax time. But if it’s a significant difference, it’s in your best interest to update your income projection in your Marketplace account.

The Marketplace can then adjust your APTC amount, either up or down, to reflect your new income projection. If you’re earning less than you thought you would (but still in the subsidy-eligible range), your APTC will increase, making your net premiums lower and more affordable for the rest of the year. This might be preferable to waiting until tax time to recoup that additional subsidy amount.

If you’re earning more than you thought you would earn, the Marketplace will reduce (or eliminate, if necessary) your APTC. The alternative is having to repay all of the excess when you file your taxes.

APTC repayment calculatorTool


Source link

Health Care in the 2026 Midterm Election


rewrite this content and keep HTML tags

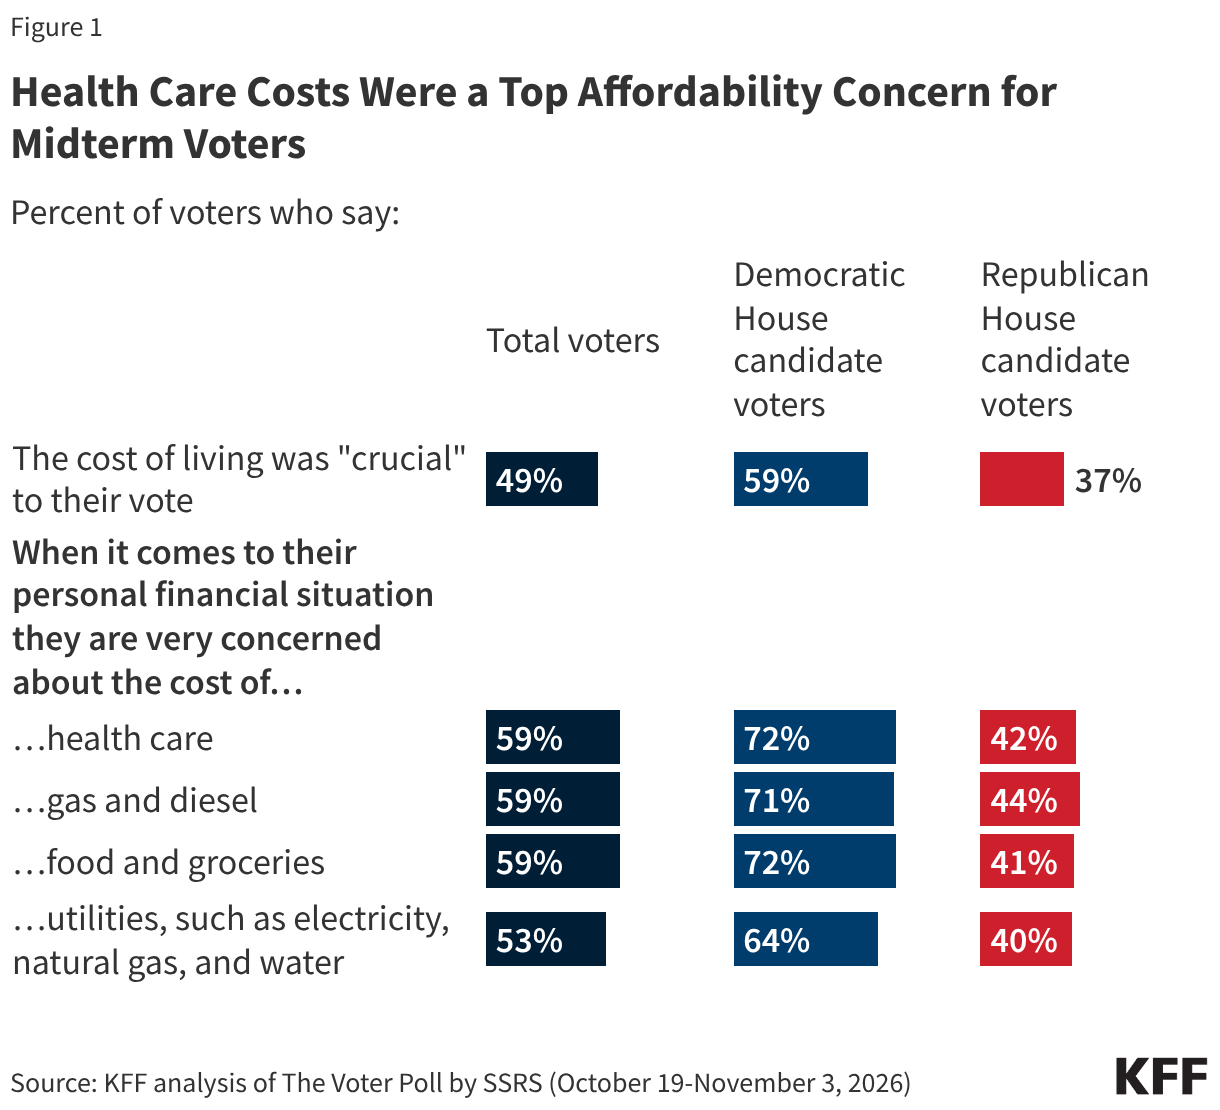
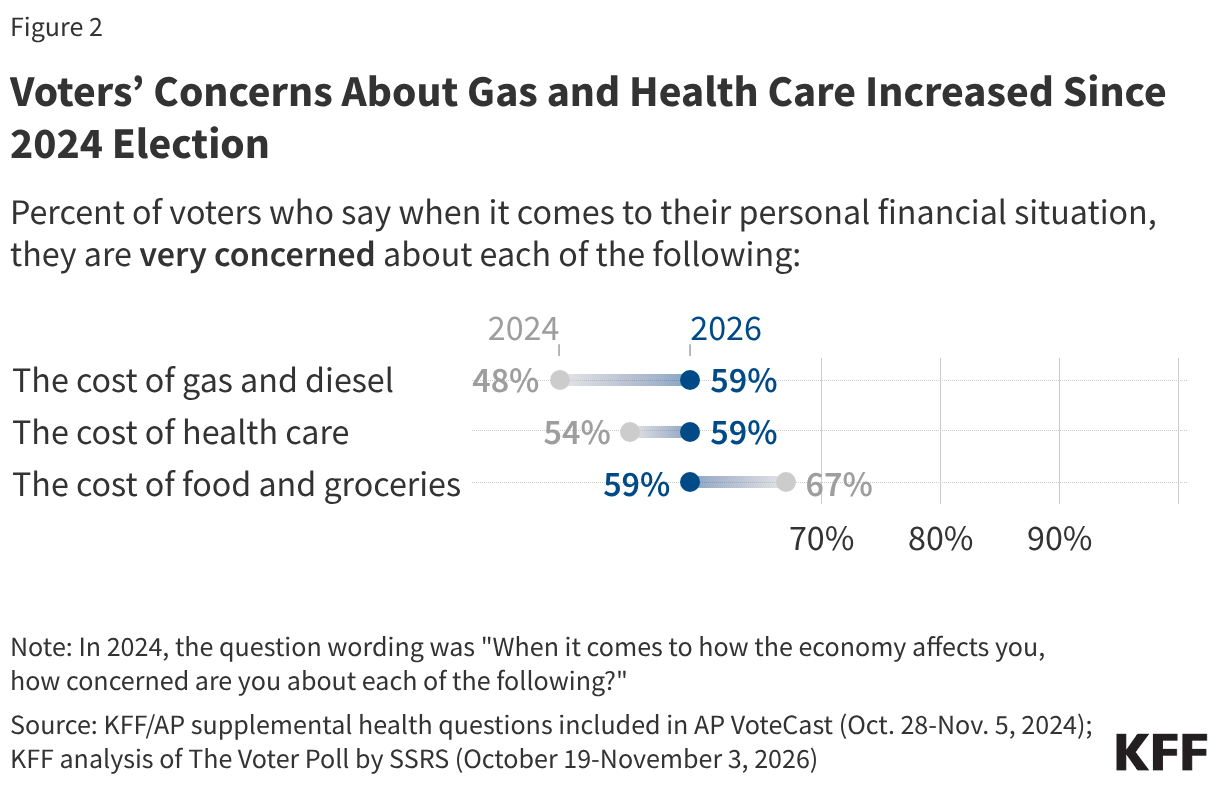
The cost of living was a top issue on voters’ minds this election, and health care costs played a key role in voters’ cost of living concerns alongside concerns over affording other essentials like gas and groceries. Among voters overall, about half said the cost of living was “crucial” to their vote for Congress, rising to about six in ten among those who voted for Democratic House candidates compared to fewer than four in ten who voted for Republican House candidates. Among voters overall, about six in ten said that when it comes to their personal financial situation, they were “very concerned” about gas and diesel, health care, food and groceries, while slightly fewer said the same about utilities. Among those who voted for Democratic House candidates, about two-thirds or more said they were concerned about the costs of these essentials, while fewer, about four in ten voters for Republican House candidates, said the same.   


Health Care Costs Were a Top Affordability Concern for Midterm Voters (Split Bars)

Compared to those who voted in the 2024 presidential election, voters’ concerns about the cost of gas and diesel were eleven percentage points higher in this election, and concerns about health care costs rose by five percentage points. At the same time, the share of voters who were “very concerned” about food and grocery costs declined by eight percentage points.


Range plot showing percent of voters who said they are very concerned about various expenses. Results shown among voters in 2024 and 2026.

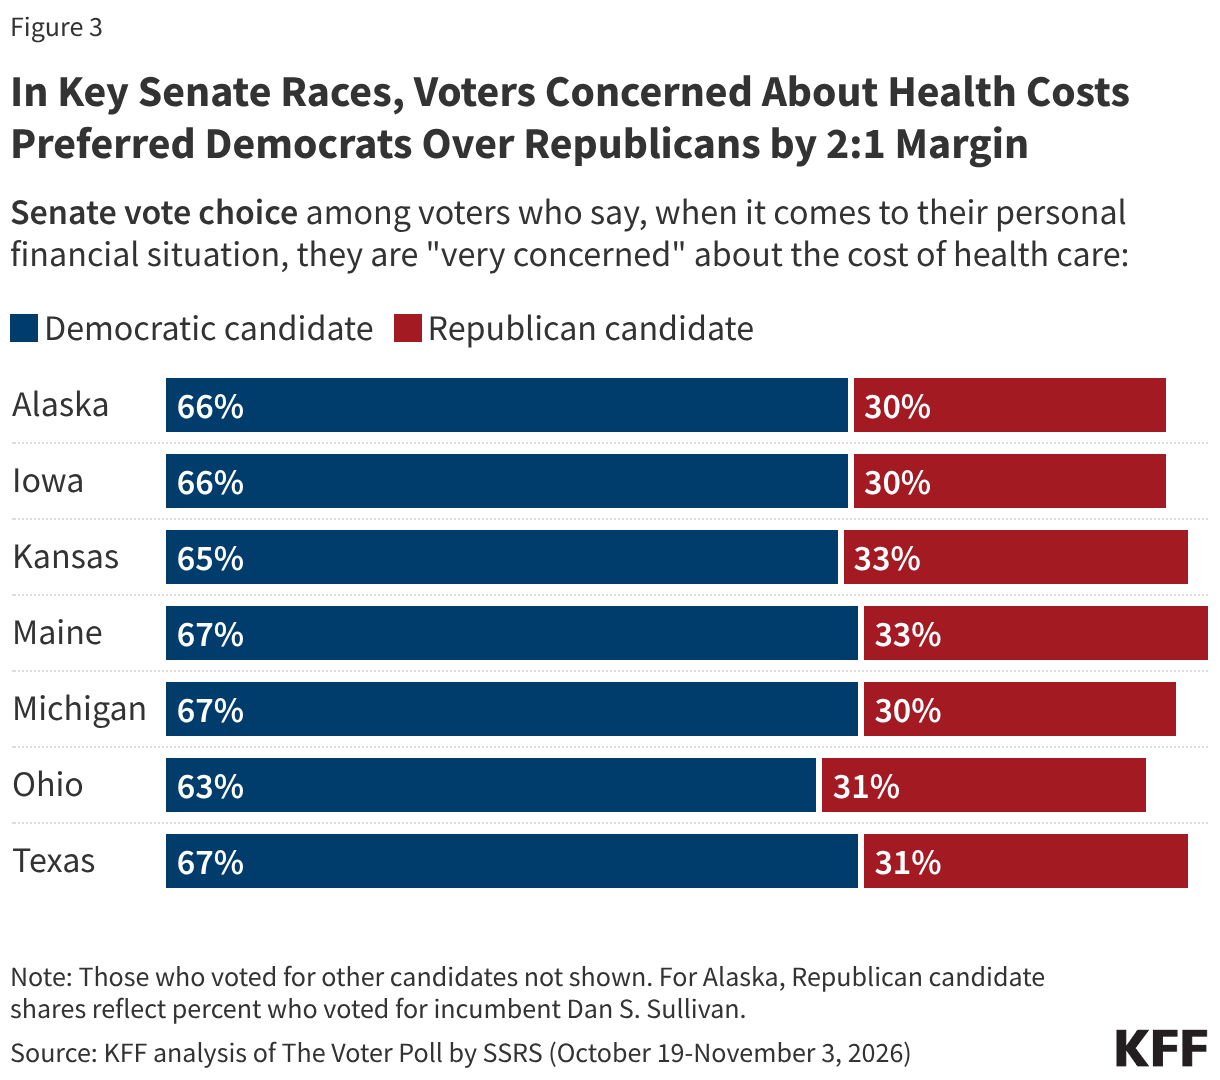
Democratic Senate candidates had a strong advantage among voters who were concerned about the cost of health care in key battleground states. About two-thirds of voters who were “very concerned” about health care costs said they voted for the Democratic Senate candidate across 7 states, while about three in ten of this group said they voted for the Republican Senate candidate. This reflects a reversal of dynamics from the 2024 presidential election, when voters who expressed similar cost concerns about health care favored President Trump over Vice President Harris by a ten-point margin.  

Stacked bar chart showing percent of voters from various battleground states who voted for either the Democratic or the Republican candidate. Results shown among voters who are very concerned about the cost of health care.

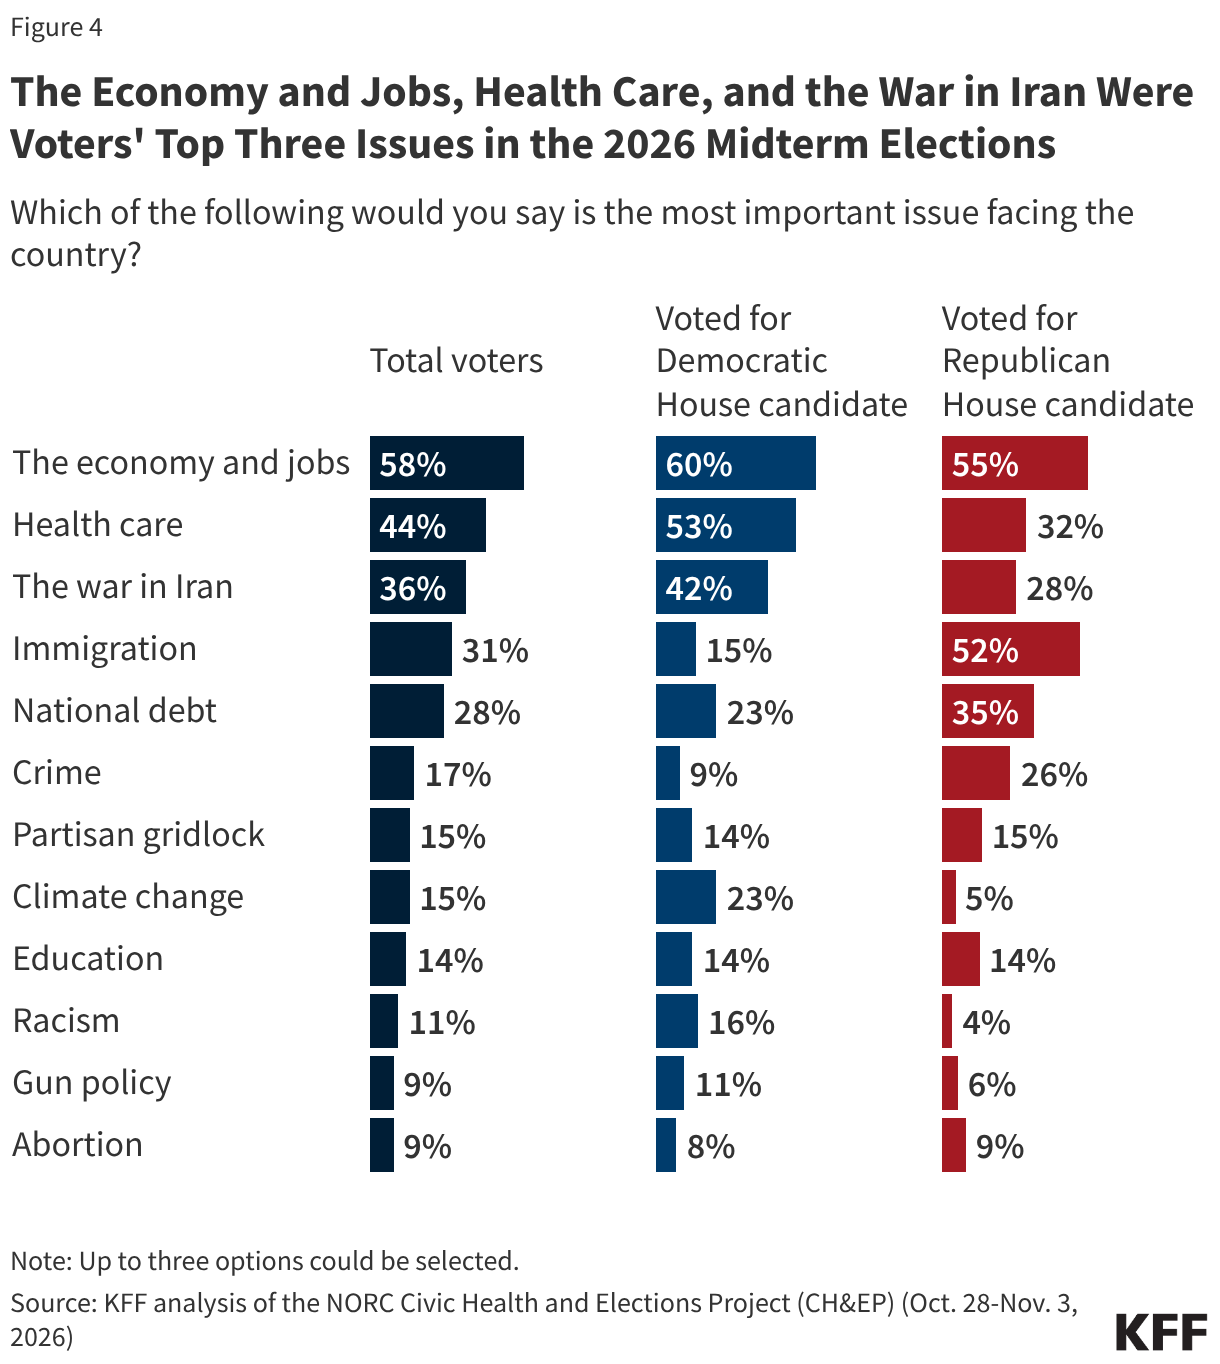
As with most previous elections, the economy was the number one issue in the 2026 midterms, with about six in ten voters overall saying “the economy and jobs” was the most important issue facing the country. While many polls ask voters to choose only one issue, NORC’s Civic Health and Elections Project poll allowed voters to choose up to three issues from a list, and health care was the second most selected issue among voters overall, with about four in ten saying it was an important issue. Health care was the second highest ranked issue for voters who said they voted for a Democratic House candidate, whereas more voters who chose Republican House candidates chose immigration as a top issue.  

Split bar chart showing the most important issue for voters. Results shown among total voters and voters by which political party's candidate they voted for in the House election.


Source link

Explaining Health Savings Accounts in the Affordable Care Act Marketplaces


rewrite this content and keep HTML tags

This brief examines how the budget reconciliation law expanded access to HSA-eligible plans and accounts on the ACA Marketplaces and what these changes means for enrollees. Health Savings Accounts (HSAs) are tax-advantaged savings accounts that enrollees in certain high-deductible health plan (HDHPs) can use to pay for qualified medical expenses.

HSA-compatible plan options have grown substantially since the law took effect, creating both benefits and risks for consumers. For example, Marketplace enrollees could benefit from the tax advantages of contributing to an HSA—but doing so requires enrolling in a high-deductible plan and anticipating future health care costs and income.

The brief is part of the Peterson-KFF Health System Tracker, an online information hub dedicated to monitoring and assessing the performance of the U.S. health system.


Source link

Are Employer Health Costs Out of Control?   


rewrite this content and keep HTML tags

Conventional wisdom has it that employer health costs are out of control. That builds on the general angst about health costs. Bad news also gets attention, and hyperbole justifies the efforts  of large health benefits teams at companies. For some, painting the employer system as broken is a subliminal case for single payer. Employer health costs have certainly been out of control in the past when we saw double-digit annual increases in employer health premiums—one year way back in the 1980s they rose 18%—but what about lately? 

What the data actually show is that employer health costs have been rising moderately in recent years. They are a problem, but not out of control. And the big story in 2026 was that employers chose to stick workers with a big increase in what they pay for premiums despite fairly moderate increases overall.  

I have been studying this issue and writing about it since my days at MIT decades ago. Here are the key data from our annual benchmark employer survey and my assessment of what is going on.  

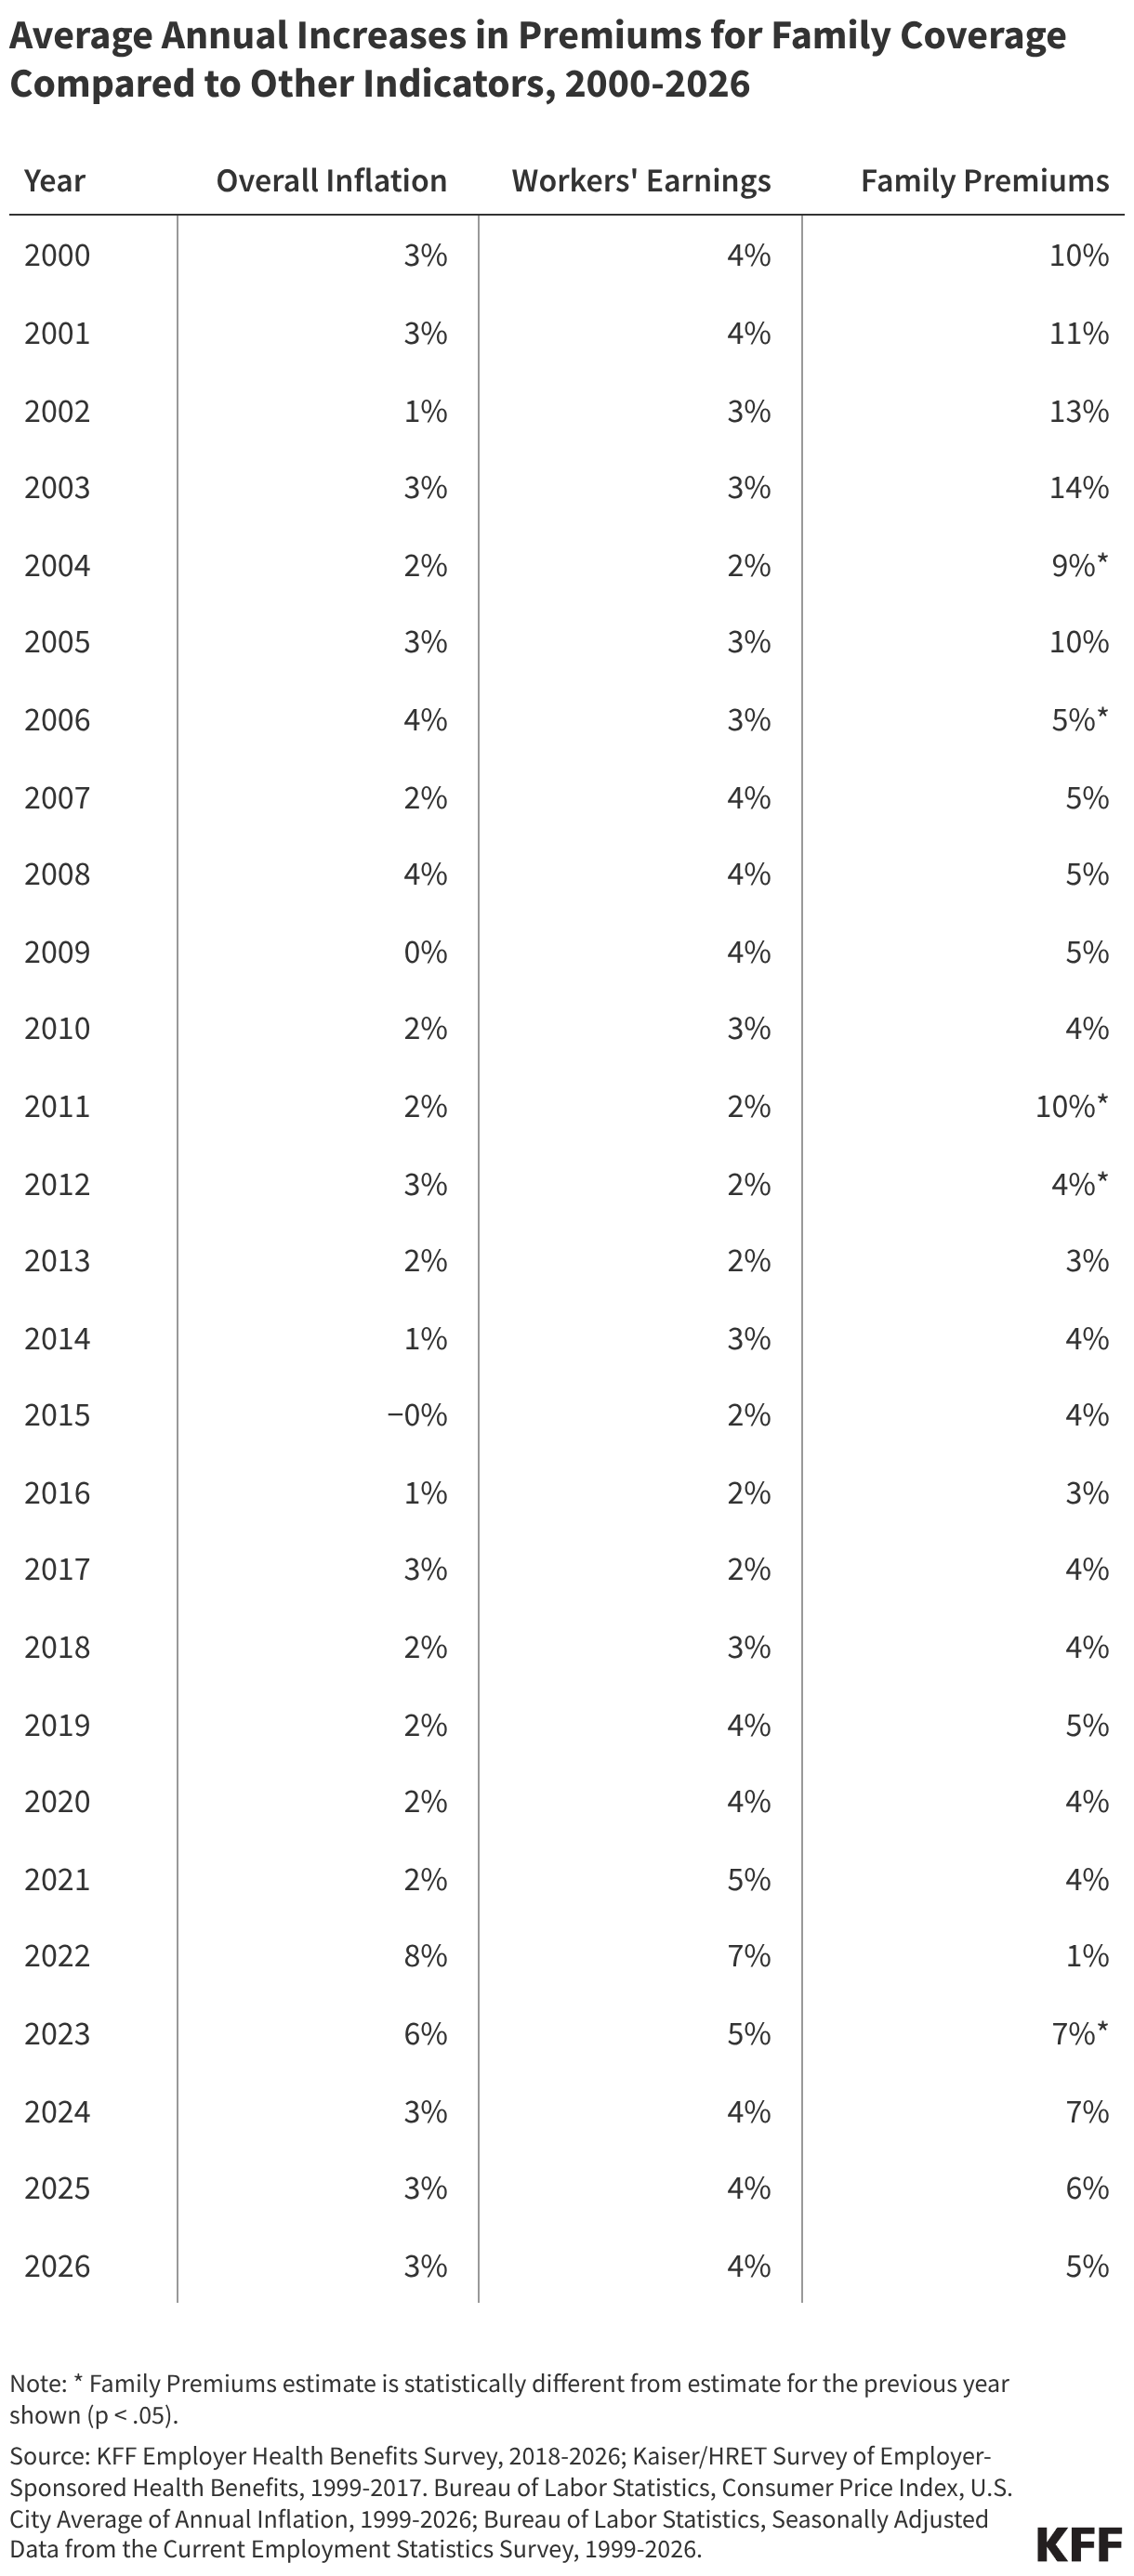
On average, employer premiums rose 1% in 2022, 7% in 2023 and 2024, 6% in 2025, and 5% in 2026. These are substantial increases but far from the double-digit increases we saw back in the early 2000s, and short of the increases that benefits officers always tell consulting firms to expect. There is always a difference between the urgency that benefits officers and CEOs feel about health costs, and I doubt very many CEOs are having sleepless nights about a 5% premium increase given all the other problems they face. 

Average Annual Increases in Premiums for Family Coverage Compared to Other Indicators, 2000-2026 (Table)

It’s possible that our reported 5% increase is low this year. It’s based on a survey, and sometimes surveys have statistical errors. Five percent “feels” low to me. However, it’s similar to recent increases, which also surprised me. That’s why we do the survey to get real numbers, but as rigorous and transparent as we can be in our methods, sometimes a survey is just off.

Still, modest increases add up, and with the cost of the average family policy passing $28,000 a year, providing coverage is a big lift for any employer.  

With no silver bullet and limited market power, most employers typically do a little of everything to stem rising costs, stopping short of steps that would generate too much employee blowback. Smaller employers are basically helpless and take what they can get.

In a year with a moderate overall premium increase, it was surprising to see the worker share of premiums rise 9% this year, almost twice the rate of increase in employer premiums and three times the rate of inflation. (Employers still shoulder most of the overall bill, on average about 75% for family coverage and more for individual coverage.) 

And, unlike increasing deductibles and other forms of cost sharing, which also adds to workers’ economic pain, increasing the share of premiums doesn’t impact underlying health costs by influencing health seeking behavior. 

Time will tell, but this could signal that many employers feel the “fancier” cost strategies they have been using are played out. As a CEO, I know that nothing produces bottom-line savings faster for an employer than offloading premium costs, which we have resisted at KFF.  Another step with immediate results looking forward: not covering expensive new drugs. Our survey shows that most employers are not covering GLP1s for weight loss.

One hundred and sixty million people are covered by employer-based insurance. Add the higher costs they are paying for premiums to the increased costs people are paying in the ACA Marketplace plus the new work requirements hitting in Medicaid and other Medicaid cuts and higher Medicare costs for many beneficiaries this year, and you begin to piece together why there is such a widespread sense of an affordability crisis in health care right now.  

In any event, the story this year is not about out-of-control employer health costs—they were moderate—or of a collapsing employer-based insurance system, although it certainly has many problems, including being propped up by a $470 billion annual tax subsidy. Instead, the story this year seems to be a conspicuous shift of premium costs to workers despite a moderate overall premium increase. 

View all of Drew’s Beyond the Data Columns


Source link

9 Things to Watch for the 2027 ACA Open Enrollment Period 


rewrite this content and keep HTML tags

The Affordable Care Act (ACA) Marketplace 2027 Open Enrollment period starts November 1, 2026, in most states. In 2026, the enhanced premium tax credits expired, provisions of the 2025 budget reconciliation law (the “One Big Beautiful Bill Act”) began to take effect, and Trump administration regulations began to change Marketplace coverage, with effects expected to carry into 2027 enrollment. Further changes in the ACA Marketplaces are again expected in 2027.

Here are the nine things to know for the 2027 Open Enrollment period:

1. Premiums are going up by double-digits, but most people get a subsidy.

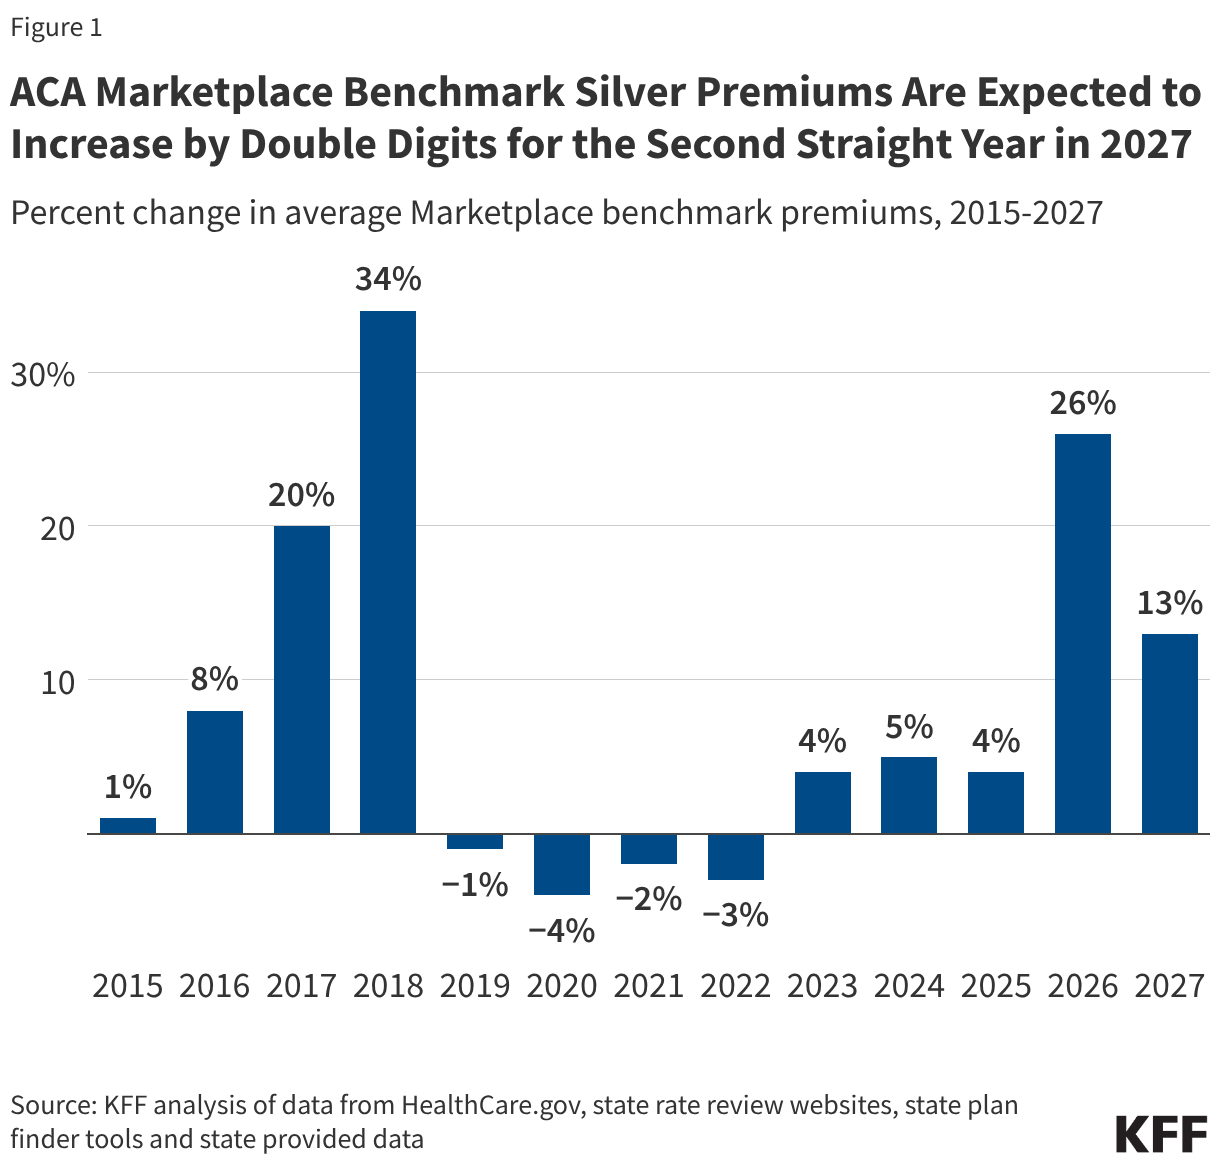
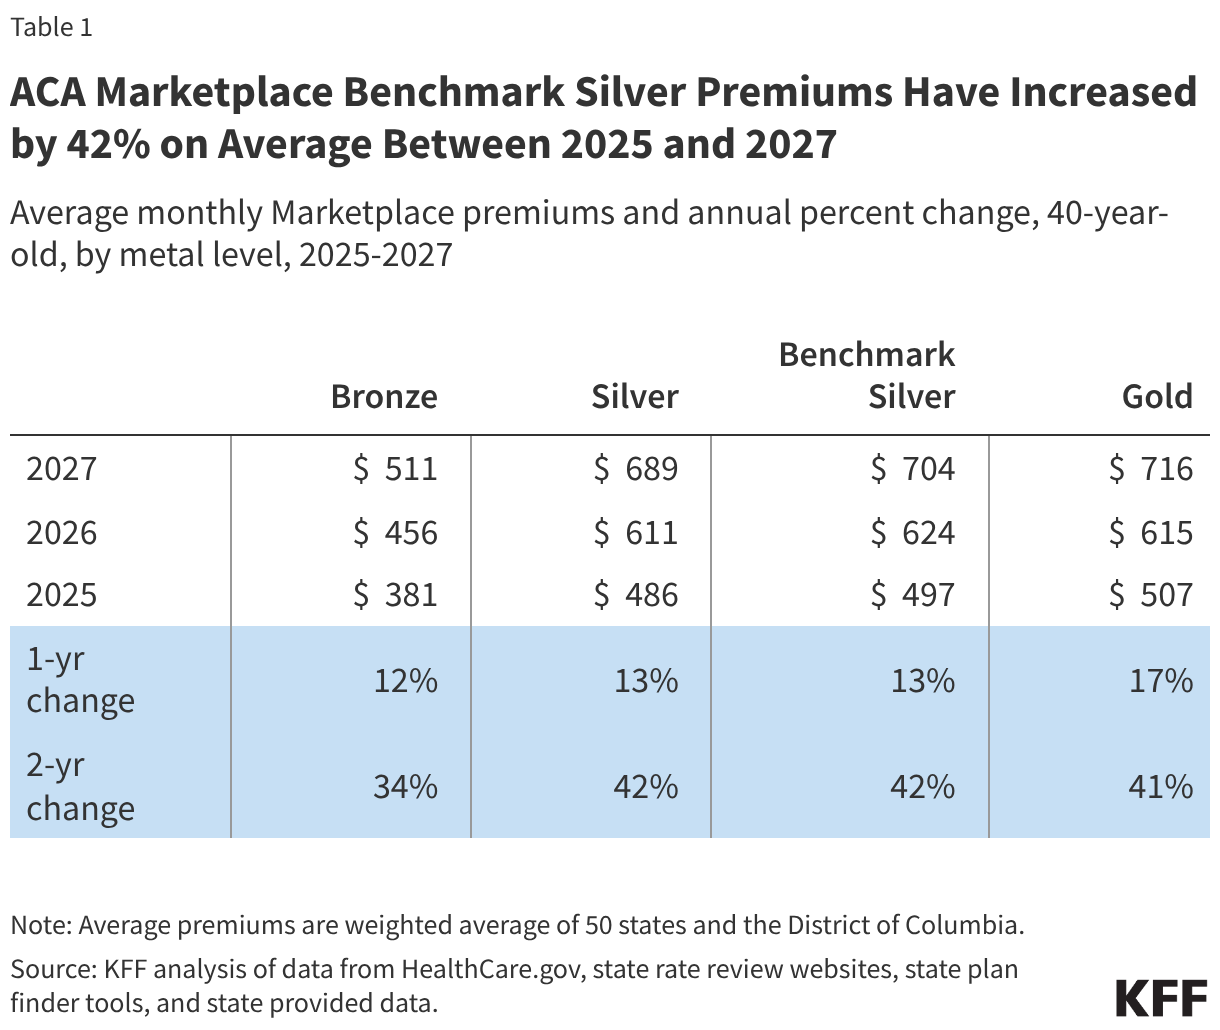
While insurers proposed a median premium increase of 15%, the average increase in finalized benchmark silver premiums for 2027 is 13%, marking a second consecutive year of double-digit proposed increases (these premiums rose by 26% from 2025 to 2026). In states that use the Healthcare.gov platform, benchmark silver premiums are increasing 11%, whereas states that run their own enrollment platforms are seeing premium increases of 16%. From 2025 to 2026, HealthCare.gov states saw a 30% increase, whereas state-based Marketplaces saw a roughly 17% increase in benchmark premiums.

ACA Marketplace Benchmark Silver Premiums Are Expected to Increase by Double Digits for the Second Straight Year in 2027 (Column Chart)

In their rate filings, insurers point to a higher-than-usual increase in the underlying cost of care, which is not unique to the ACA Marketplaces; some employer plans have also seen steep cost increases.

ACA Marketplace insurers also cite the expiration of the enhanced premium tax credits and the resulting changes in the risk pool as factors contributing to higher premiums. KFF’s analysis of insurer filings found that insurers estimated risk pool changes added about four percentage points on average to premiums in 2026 and expect a similar, additional effect in 2027.

Most enrollees get a subsidy that will cushion the impact of these increases in 2027. However, people with incomes above 400% of the federal poverty level (FPL) will be particularly hard hit because they no longer qualify for premium tax credits and must pay the full cost of coverage. Sharp premium increases in 2027 follow even steeper increases going into 2026. These higher costs may lead additional healthier enrollees to drop coverage, further worsening the risk pool and putting additional upward pressure on premiums.

ACA Marketplace Benchmark Silver Premiums Have Increased by 42% on Average Between 2025 and 2027 (Table)

2. Marketplace enrollment is declining following the expiration of enhanced premium tax credits, and may continue to fall for other reasons.

Enrollment in the ACA Marketplaces declined following the expiration of the enhanced premium tax credits. During the 2026 Open Enrollment Period, Marketplace plan selections fell by 1.2 million from 2025. By February 2026, effectuated Marketplace enrollment (i.e., people who pay their premiums and remain enrolled) was down 12% (or 2.6 million people) from the previous year to 19.2 million people. More recent Marketplace-specific enrollment data are not yet available, but enrollment data for the individual market suggest the decline may have continued through the first half of 2026. Data for the broader individual market, which includes both Marketplace coverage and plans purchased directly from insurers or brokers, show a continued decline. Individual market enrollment fell 18% by June 2026, from 25.2 million to 20.5 million people—a loss of more than 4.6 million.

Looking ahead to 2027, several insurers have said they expect the market to continue to deteriorate in 2027 as a continued result of the enhanced premium tax credits ending. Some enrollees who were able to keep coverage in 2026 may no longer be able to make ends meet.

As discussed more below, anti-fraud efforts and changes to eligibility for tax credits affecting certain immigrants will also have a downward effect on Marketplace enrollment. In its latest projections, the Congressional Budget Office (CBO) estimated ACA Marketplace enrollment would fall from a peak of 22.4 million in 2025 to 13.1 million in 2027.

3. Insurer exits outnumber new entrants.

The number of insurers participating in the ACA Marketplaces is expected to decrease again in 2027, with more insurers announcing plans to exit the Marketplace than to enter. As of October 29, 2026, 11 carriers had announced plans to exit at least one state for 2027, while seven carriers had announced plans to enter a new state. Shrinking Marketplace enrollment after the expiration of the enhanced premium tax credits has reduced the potential market for insurers and raised concerns about the future of the risk pool. The changes will vary across states, but in some areas, consumers will have fewer insurers to choose from in 2027. Cigna, for example, is leaving the individual market in all 11 states where it currently participates.

Insurer exits can reduce competition and leave consumers with fewer choices of plans and provider networks and disrupt coverage for some enrollees.

4. Some state-based Exchanges have backfilled lost enhanced federal tax credits.

Some states that operate their own Exchanges are using state-funded subsidies to help offset the expiration of the enhanced premium tax credits, with several continuing or expanding assistance in 2027. New Mexico went furthest in 2026, fully backfilling the lost federal assistance for Marketplace enrollees. While enrollment declined nationally, New Mexico saw Marketplace enrollment grow during the 2026 Open Enrollment Period. The state is continuing its assistance in 2027.

Other states provided more limited assistance in 2026 and may expand eligibility in 2027. California, for example, is continuing state-funded premium subsidies but is expanding its program to partially backfill lost enhanced tax credits for households with incomes between 165% and 200% FPL. Previously, only households with incomes between 138% and 165% FPL were eligible for state assistance to replace any portion of the expired enhanced tax credits. Several other states have also maintained subsidy programs such as New Jersey, while Rhode Island and Virginia moved to create new state-specific subsidies for the 2027 plan year. These state efforts may help some consumers afford coverage despite the loss of federal assistance, but the amount of support available varies by state and income.

5. Recent federal actions to address fraud may affect enrollment counts and make it more difficult for enrollees needing brokers’ services in 2027.

Recent initiatives to combat Marketplace broker fraud could impact counts of the number of enrollees this Open Enrollment cycle, the availability of enrollment assistance, and certain agent and broker practices in 2027. Some provisions that attempt to address fraud by placing new requirements on consumers have been temporarily paused due to court action (discussed more below).

In September 2026, HHS reported they cancelled coverage for approximately 760,000 individuals who CMS says were “phantom” enrollees, meaning a broker or agent may have signed them up without their knowledge. HHS sent a list of about 1.2 million people to insurers to review. These individuals had been signed up by an agent or broker, had no premium payment and were missing a Social Security number or immigration document that could be verified in real time. If insurers were unable to make contact with these individuals or verify they had incurred claims, CMS cancelled the coverage. There are reports that some enrollees have had their coverage reinstated suggesting that the criteria CMS used to identify potential fraud may have also flagged legitimate enrollees. Others who lost coverage through these efforts may not have their coverage restored.

Additionally, HHS is implementing new safeguards on certain agents, brokers, and web-broker practices that put consumers at risk of inappropriate or fraudulent enrollments. This follows investigations of brokers and other related entities moving enrollees to different plans or enrolling them in Marketplace coverage without their knowledge. For instance, the HHS Notice of Benefit and Payment Parameters for 2027 updates standards of conduct for agents, brokers, and web-brokers regarding prohibited marketing tactics, including but not limited to providing cash, monetary rebates, or cash equivalents to persuade consumers to enroll in coverage; falsely claiming that consumers will always qualify for zero-dollar insurance or zero-dollar premiums; and providing false information on enrollment timelines and deadlines. Agents, brokers, and web-brokers must submit marketing materials to HHS upon request in response to monitoring, auditing, or enforcement activities. Agents, brokers, and web-brokers that contract with a third party or other entity to produce marketing materials must ensure that those entities follow the requirements that apply to agents, brokers, and web-brokers.

In September 2026, HHS announced an even more stringent restriction that temporarily pauses the registration of new agents and brokers in the federally facilitated Marketplace and for Marketplaces that operate on the federal platform until February 2027. CMS estimates that approximately 19,000 new agents and brokers would have registered absent the temporary restriction. Combined with the reductions in Navigator funding for 2026 announced in February 2025, consumers may have less access to enrollment assistance in 2027.

6. Some lawfully present immigrants will no longer qualify for subsidized Marketplace coverage in 2027.

Currently, subsidized ACA Marketplace coverage is available to lawfully present immigrants. Lawfully present immigrants include lawful permanent residents (LPRs or green card holders), people on work visas, and humanitarian immigrants such as refugees, victims of human trafficking, asylees, among others. Undocumented immigrants are not eligible to purchase ACA Marketplace coverage, even at full cost. While immigration statuses eligible to purchase ACA Marketplace coverage have not changed for 2027, the 2025 budget reconciliation law limits eligibility for tax credits in the Marketplace to only certain groups of lawfully present immigrants including:

  • Lawful permanent residents
  • Cuban and Haitian entrants, as defined in section 501(e) of the Refugee Education Assistance Act of 1980
  • Any lawful residents living in the U.S. under the Compact of Free Association

Other lawfully present immigrants such as refugees, victims of human trafficking, and asylees, can still purchase Marketplace coverage but will no longer be eligible for premium tax credits. Without subsidies, many may be unable to afford their premiums and could drop coverage. CBO estimates that one million more individuals will be uninsured as a result of this provision by 2035.

7. Enrollees will face the elimination of repayment limits.

Beginning in the 2026 tax year, limits that previously capped how much some Marketplace enrollees had to repay in excess premium tax credits were eliminated as enacted through the budget reconciliation law (“The One Big Beautiful Bill Act”). Because the first tax filings under the new rules will not happen until early 2027, enrollees will choose 2027 plans without having seen how uncapped repayment works in practice. Those whose incomes end up higher than projected may face larger tax bills than they expect, and accurately estimating income and updating it when circumstances change will be especially important for people near income thresholds for premium tax credits or cost-sharing reductions.

Some enrollees may be able to lower their modified adjusted gross income (MAGI) through contributions to accounts such as health savings accounts (HSAs) or traditional individual retirement accounts (IRAs). These contributions could increase premium tax credits or help people near 250% FPL qualify for cost-sharing reductions (CSRs). However, HSA contributions are available only to people enrolled in HSA-eligible plans, and not everyone has the funds to contribute. Because Marketplace assistance is based on projected annual income, enrollees considering this approach may also need to update their income estimates during the year.

8. Consumers who are denied or removed from Medicaid coverage for not meeting work requirements will also be ineligible for premium tax credits.

Starting in 2027, in states required to implement Medicaid work requirements, consumers who lose or are denied Medicaid coverage solely for not meeting work requirements will also be ineligible for subsidized Marketplace plans in these states. Prior to the budget reconciliation law, a consumer who was denied Medicaid coverage or disenrolled from Medicaid could sign up for Marketplace coverage as long as they met Marketplace eligibility requirements. Because income eligibility for Medicaid references a monthly income whereas Marketplace premium tax credits are based on an estimated annual income, consumers may be concurrently eligible for both, especially in Medicaid expansion states. While this is likely a small group of people, it may include individuals who recently lost a job and who would likely not meet the Medicaid work requirements.

When the budget reconciliation law was signed, only Georgia had Medicaid work requirements in place; the law now requires 43 states and the District of Columbia to implement work requirements by the start of 2027. Exclusion from ACA tax credits based on failing Medicaid work requirements will apply to adults in Medicaid expansion states and those that are covered under Medicaid Section 1115 waiver programs to expand coverage. People who lose Medicaid coverage as a result of these requirements, including those who are working or qualify for an exemption but fail to navigate reporting rules, may face challenges finding affordable coverage because they will remain ineligible for premium tax credits until they are no longer eligible for Medicaid for reasons other than not meeting work requirements (such as a change in income).

9. Litigation has halted implementation of some Marketplace requirements for 2027.

Litigation challenging two final regulations that make substantial changes to Marketplace requirements – the 2025 program integrity rule and the HHS Notice of Benefit and Payment Parameters for 2027 – have halted implementation of many new rules for the time being. Four key cases are working their way through the courts: The 2025 program integrity rule was challenged in City of Columbus et al. v. Kennedy (Columbus I) and California et al. v. Kennedy (California I). Litigation over the 2027 Payment Notice is also ongoing in City of Columbus et al. v. Kennedy (Columbus II) and California et al. v. Kennedy (California II), with some provisions of the 2027 Payment Notice stayed as the litigation continues.

The state of play after several court decisions over the past year include the following:

  • Failure to reconcile requirement: For plan year 2027, consumers will not be disqualified from receiving premium tax credits if they fail to file and reconcile prior years’ premium tax credits. So, for example, an enrollee who failed to file their tax return and reconcile for the 2025 tax year in 2026, will not lose subsidies for 2027 coverage.
  • Expansion of eligibility for catastrophic plans: A 2025 announcement expanded who can enroll in catastrophic plans, allowing individuals who were not eligible for premium tax credits or other cost-sharing help because their projected income was below the federal poverty level or above 250% FPL to sign up for catastrophic coverage. This expanded eligibility has been temporarily paused due to a June decision in Columbus II. This means only a narrow group of people including individuals under age 30, those whose Marketplace or employer coverage would cost more than 8.5% of their income, and those who qualify for a hardship exemption can enroll in these plans during open enrollment.
  • Other requirements are not in place for now or have been vacated. Due to litigation, CMS has stated that it will not implement a long list of final requirements. This includes certain income verification requirements, network adequacy requirements, and the elimination of standardized health plans. In addition, other requirements, including an Administration rule that would prohibit states from including gender-affirming care as an essential health benefit and a rule that would have shortened the Open Enrollment Period to nine weeks, have been vacated.


Source link

The Average Monthly Premium for Medicare Part D Stand-Alone Plans Is Projected to Increase by 50% From $34 to $51 in 2027 Unless Enrollees Switch to Lower-Cost Plans 


rewrite this content and keep HTML tags

A new KFF analysis finds that the average monthly premium for Medicare Part D coverage in stand-alone prescription drug plans (PDPs) will increase to $51 in 2027, up 50% from $34 in 2026, if current enrollees don’t switch into lower-premium plans during open enrollment, which runs through December 7.  

The analysis of premium and cost-sharing requirements for Part D coverage in 2027 also finds that the projected average monthly premium of $51 for PDPs is more than five times higher than the drug coverage premium in Medicare Advantage plans that offer Part D coverage (MA-PDs), which is projected to average $9 per month next year. The estimated $17 increase in the average monthly PDP contrasts with an expected increase of less than $2 in monthly premiums for drug coverage through MA-PDs. 

“With some plans increasing premiums substantially, the stakes are higher this year for people with Medicare stand-alone drug coverage if they sit on the sidelines during open enrollment,” said Juliette Cubanski, a vice president and director of the Program on Medicare Policy at KFF. “There are relatively low-premium PDP options, but people facing large premium increases need to take action if they want to avoid paying significantly more.”  

Most PDP enrollees who are not receiving extra financial subsidies provided to low-income enrollees will pay higher premiums in 2027 if they don’t switch to cheaper plans, including more than 4 million enrollees who are currently enrolled in PDPs that charge zero premium. This is because there are no zero premium PDPs available in 2027.

Average monthly premiums for the eight national PDPs are projected to range from around $6 to $204 in 2027. The lowest-premium national PDP is Centene’s Wellcare Value Script Rx, with an average premium of $6.50 for 2027, up from $5.80 in 2026. The highest-premium national PDP is United’s AARP Medicare Rx Preferred, with an average monthly premium of $204.50, up from $126.00 in 2026.    

The analysis also finds that most Part D enrollees will face a deductible of several hundred dollars for drug coverage in 2027, including 85% of MA-PD enrollees (up from 80% in 2026) and virtually all PDP enrollees (99.8%, up from 96% in 2026), based on enrollees keeping their current plans. In 2027, Part D plans are allowed to charge a deductible up to $700, an increase from $615 in 2026, but can charge a lower amount. On average, the Part D deductible in 2027 will be $643 for PDP enrollees (up from $540 in 2026) and $489 for MA-PD enrollees (up from $360 in 2026).  

Most Part D enrollees also will face coinsurance rather than copayments for both preferred brands and non-preferred drugs, which can mean less predictable out-of-pocket costs.   


Source link

National Academy of Medicine’s 2026 Annual Meeting (Scientific Symposium on Chronic Disease)


rewrite this content and keep HTML tags

Note from Drew Altman: On October 10, 2026, I had the honor of delivering the keynote address at the annual meeting of the National Academy of Medicine (NAM), where I am a member and former member of the Institute of Medicine (IOM) Governing Council. As the event drew closer, I asked to convert the formal remarks to a fireside chat, feeling that format is more accessible to audiences. The discussion was moderated by the program head for the day, Brendan Lee, MD, PhD, the distinguished – in title and in fact – professor and chairman of the Department of Molecular and Human Genetics at Baylor. Subsequently, many requested that I write down what I had said that day, which I have done with as much fidelity to what I actually said as possible. The program focused on chronic disease, and I had been asked to paint the policy and political environment and discuss how chronic illness fits.

The Health Policy Agenda and Where Chronic Illness Fits

A long time ago in government, I was described in a major newspaper as “a nice guy trapped in a deadly serious face.” So, I hope it shines through the mask what a special privilege it is to be the first Victor Zau Keynote speaker this year. Victor has always led with science, values, transparency and tremendous honor.

He led through a transition from IOM to NAM that I was on the other side of, feeling it was a mistake for IOM to lose control of so many of its substantive programs, even co-authoring a dissenting report when I was on the Governing Council, but I have nothing but admiration for how Victor has guided us through the changes, and now we have superb new leadership at the Academy, which we just witnessed in action.

I have transitions on my mind, making my own after 37 years since founding KFF.

A million years ago, when I received a PhD in political science at MIT, I received a note from my 96-year-old grandmother which simply said: “Congratulations, so what are you going to do, open a political science store?” Those of you who know KFF know I sort of did. I started what is now KFF back in the early 1990s based on a simple idea: Health was becoming a bigger issue and the country would need a trusted independent source for health policy information. We do that by doing lots of policy analysis, polling and survey research, and through our newsroom, now the largest health newsroom in the country, with bureaus across the U.S. We are not a policy research shop, although we do tons of policy research. We are not a polling organization, although we are well known for that. Nor are we a news organization. We are a “unicornish” combination of all three, and it’s the combination of all three, coordinated and focused on the same issues, that gives us the power and presence to play our national role and reach the different audiences we want to reach. For those of you who may remain confused about this: We do not have and never have had any connection to Kaiser Permanente, and we are not a foundation. We are a public charity – or endowed nonprofit – based in San Francisco.

One important thing about us is that we never take positions or make recommendations, but I certainly understand that data and analysis are not neutral in national health policy. In fact, we are built to annoy all sides at one time or another, and we do.

Big health policy debates come in cycles and health policy is heating up again, driven by voter concern about cost of living and health care costs, the midterms, wins by progressive Democrats pushing more expansive reform ideas again (whether they go anywhere or not), controversial administration policies, and much more. They will continue to grow through 2028 and a potentially big legislative agenda beyond. Today, I want to talk about a few of the biggest challenges we face in health policy, and how your topic today –  chronic illness – is central to them, obviously viewed through the lens of a hard-core health policy organization. I recognize that there are lots of different folks here with different perspectives and NAM has its own priorities, and I have no quarrel with that. There will be overlap, but we are a different animal in health policy.  

There are three problems I want to talk about:

  • Rebuilding Medicaid and Affordable Care Act (ACA) coverage after almost a trillion dollars in cuts in federal spending in the two programs over the next 10 years, the largest cuts in coverage and federal health spending in our history.
  • Reconstructing federal agencies – a task which is receiving inadequate attention and will mean daunting decisions about funding, staffing, and most challenging of all – redesigning what agency missions should be. Lest we forget, nobody was happy with the primary Health and Human Services (HHS) agencies before, but we are so unhappy with the state of affairs now we forget that.
  • And third, there is a new zeal to take on health care costs. But what do we even mean by that? Have we discovered the courage we never had before to do it, and, in particular, to take on underlying costs driven mostly by hospital spending and high prices?
  • Finally, a bonus theme: we can’t deal effectively with any of this unless we make some progress restoring trust in evidence and facts, and the people and institutions that convey them, especially government scientific agencies. I am more optimistic than many people about this big challenge based on our survey data, and I will touch on that.

Two points weave in and out: 1) these challenges will compete for space on the agenda and funding. No president, secretary, or new Congress will take them all on simultaneously in a meaningful way and 2) I have written often, there is an invisible crisis of costs and affordability affecting the chronically ill and people with major diseases. And I don’t use the over-used word “crisis” lightly. It’s why I am so pleased with your focus today.

To start…

The One Big Beautiful Bill (OBBB) included almost a trillion dollars in cuts in federal health spending over ten years. Then, following on the heels of that, was the failure to extend the ACA enhanced premium tax credits, which our widely cited analysis showed, on average, doubled premiums for almost 24 million enrollees, leading millions to drop coverage and driving many more into plans with big deductibles averaging 7k a year. Effectively that’s not insurance if you drive an Uber or work in hair salon or work on a farm and make, say, 35k a year. (Fun KFF fact: 1/3 of farmers and ranchers get their coverage through the Marketplaces.)

All told, estimates are that these cuts will result in about 14 million more uninsured people over the decade, reversing progress made in recent years and bringing the number of uninsured back up to close to 40 million. But that’s not the only effect.

As a former state Human Services Secretary, I can tell you that states will try to replace some but far from all of these cuts, especially blue states. When they do, something else in the state budget will have to give. It may be education or higher education or environmental protection or corrections. Few to none will raise taxes.

The single biggest cut—330 billion over 10 years—comes from the Medicaid work requirements, a popular but highly questionable policy.

  • It’s popular because Americans love the idea of work and personal responsibility. Medicaid work also draws on a conservative view of Medicaid dominating current policy as a “welfare program,” a dividing line between Rs and Ds. Seventy-four percent of Democrats see Medicaid as a “government insurance program for low-income people.” By contrast, more than half or Republicans see it as “a welfare program.” If you view it as welfare, like cash assistance, you are likely to want to impose requirements to get it and cut it if you can. If you view it as “insurance,” you want to protect it and expand it if you can. The difference in underlying views is fundamental.  
  • I was a leader in the welfare reform movement many years ago as state human services secretary, actually for a Republican governor. I can’t stress enough how different this is from what I thought I was doing then. Welfare reform then was built on what Bill Clinton called a “reciprocal obligation.” Beneficiaries were asked to take steps towards self-sufficiency and government committed new resources to help them do that, for job training and childcare, job search and more. In my state, that meant historic new commitments to childcare and other employment-related supports. In “Medicaid work,” only the beneficiary has an obligation. That’s one reason why CBO says it produces no new work. Let me repeat that, NO new employment gains – only red tape that forces people off the rolls (5 million more uninsured says CBO). It’s a popular policy that’s a huge administrative lift for any governor, which doesn’t produce work but is popular because it sounds like it promotes work and personal responsibility.

A Second Big Challenge Is Rebuilding the Federal Agencies

I was a young academic at MIT when I got a job working for the head of what is now CMS, an agency I was later asked to run. It changed my career and my life, which became all about public service, whether in the public or nonprofit sectors. Can that happen anymore? How do we revitalize rather than demonize public service? What does it mean that 60% of the graduates of the Kennedy School go to big consulting firms (the last time I looked)?

I don’t need to tell this audience about the staffing cuts in the federal agencies, the dismantling of agencies of special relevance to this audience such as AHRQ, the warping of missions and science, including jarring recent reports from research arms of HHS asserting that enrollees dropping coverage all did so because they were there fraudulently. I have had hundreds of calls from expats from HHS looking for help and so have many of you.

Interestingly, by far the largest of the agencies in terms of budget, CMS, protected by Dr. Oz, has been largely immune from the storms that have swept through other agencies caught up in the science and culture wars.

I don’t want to present a lot of data about staffing cuts, and a lot of it is fluid and unreliable or from advocacy groups. To me, these are the critical points:

  • It will take a Marshall Project to rebuild the HHS agencies
  • No secretary will be able to do it and do everything else he or she needs to do. (I know how daunting it will be. I have been offered that job too and looked it in the eye.)
  • If plans are not made ahead of time, it will be two years into an administration before much is done, and that could be too late; likewise if it is done agency head and agency by agency over time
  • For those reasons, it would be timely for some distinguished nonpartisan group (KFF, NAM, a new commission funded by foundations) to take this on now. If I were a Secretary, I would appoint, in effect, a reconstruction czar, who would focus solely on plans and proposals for the reconstruction of CDC, FDA, the PHS agencies and NIH, including mission, staffing and funding.
  • How to formulate an updated commitment to equity across HHS will by itself be a daunting challenge, but it must be done.  

This is a tough one because no candidate will run on restoring federal agencies, but this audience understands how essential it is.  

Third, there is a new zeal to take on health care costs. But what do we even mean by that? At all the conferences I speak at, I find that we are often talking past each other as if we operate in a Venn Diagram with sets that only somewhat overlap and often conflict. Often in my world, we are talking about federal health spending. Cutting that often puts pressure on a different problem we sometimes talk about, state health spending. Employers are entirely concerned about their annual premium increases, and they should be. Our annual survey shows the average cost of a family policy is now almost $28,000 a year, the equivalent of buying a Toyota Corolla each year. Then there is “value” – a concept which encompasses at one and the same time the most forward-looking reforms in payment and delivery and the most backward rear-guard actions to forestall either real market competition or government regulation that might address underlying costs. In general, beware of any idea that is popular with everyone.

Then there are the two really big cost problems.

There is the one experts have always cared about most, national health care spending, measured as the share of GDP we spend on health care or per capita health spending. For reasons we debate endlessly in my world, health care as a share of GDP, long predicted to blow through 20% of GDP, has been pretty stable for a long time at about 18%. That’s much higher than other wealthy nations but reasonably stable. It’s predicted to rise more sharply again, and the main culprit as always is our high prices, which we don’t deal with much, focusing more on volume and utilization in bits and pieces.

And then there is the cost problem, which is driving the rising concern about health care nationally and has made health care a political issue. It’s none of the above; its “affordability” – the cost of health care to people. That—and only that—is what has made health care a voting issue.

  • If you look at the polls, the economy always emerges as the voters’ top concern. So, in our monthly tracking poll, we asked voters and I paraphrase: You said the economy was your top worry, what about the economy worries you the most? Health care costs were at the top of the list, ahead of the cost of food, housing, and even gas prices.
  • Assuming gas prices would eventually eclipse health care, we continue to ask every month and health care costs have remained number one, just ahead of gas prices, until tying with them recently.
  • But they are all closely clumped together, and it makes sense that health care costs are a top “worry” since they are less predictable than some other costs. The uncertainty makes people worry about it more.
  • The best way to understand this: voters see health care costs as one dimension of a set of inter-related cost-of-living concerns they are concerned about. It’s not number one, two or three…it’s all one concern.
  • While I am talking about the midterms, it’s also useful to always remember that issues are only one factor that drive votes. Think about your own vote. Partisan affiliation matters. The candidates and voters’ feeling about them matter a lot. Their feelings about the mood and direction of the nation and about President Trump matter (especially for turnout).  All these things matter more than issues and a lot more than candidates’ policy plans to address issues. Polling assesses these factors as well, but issue rankings tend to get featured the most.  

So, there are six different cost problems – national spending, people’s health costs, federal spending, state spending, employer premiums and value – and often we talk past each other as if they are the same. Often, they conflict: cut federal spending, for example, and you drive up state spending. The real challenge is to take on underlying costs but there is little evidence that the country has the stomach for that, nor do Democrats and Republicans have anything resembling agreement on how to do it except for some incremental measures that will have impact only at the margin. It means aggressively taking on hospital spending either through market forces (tough in a very consolidated industry) or government regulation, which is off the table with Republicans in charge and industry strongly opposed. For at least the next two years we are destined for “small ball” on costs, typically dressed up to sound more impactful than it is. A bright spot now is the action in several states to take on hospital costs.

It Turns Out that Chronic Illness Is at the Heart of the Affordability and the Complexity Problems

  • When we do surveys, we generally find that about 25% of the American people have trouble paying their health care bills and skipped or delayed care as a result.
  • Partly for this talk, we did a survey of 20,000 people looking at people with chronic conditions and serious illnesses such as asthma, cancer, heart disease, diabetes, and mental health conditions.
  • I am not going to give you a lot of numbers without slides, but for people with those conditions, the shares having problems paying their medical bills approach 40%; as many as 59% say they skipped or delayed needed care in the past year; around a quarter said their health got worse as a result; and, around a quarter said they had to cut back on other basic household needs as a result.
  • They also get caught in the health care maze more often: between 40 and 50% say their insurance company denied or delayed their care.

You could simply say, sure, of course they have the most problems; they use the most care. You could also say that the most basic obligation of any health system is to take care of people who are sick and we are not doing that. If I leave you with any big message today it is this: the chronically ill are the heart of the health care affordability crisis in the country.

But wait there’s more…

  • Again, not surprisingly, but tellingly, the worst thing you can be in our health system is chronically ill AND UNINSURED.
  • Among uninsured adults with multiple chronic conditions, 72% had problems paying or were unable to pay their medical bills. Seventy-one percent skipped or delayed needed care.
  • Forty-three percent said they got sicker as a result, and half said they had to cut back on other household needs.

To use a technical term, the chronically ill and uninsured are probably the most screwed group of all in our health system, and now with all the cuts, their ranks will grow.

Finally, I don’t believe we can make real progress without dealing with declining trust; in government agencies, the news media, medicine and science.  

We have to have shared trust in information and science. A shared belief that government can make a difference, even if we disagree over how. And a shared understanding that access to affordable health care, and health coverage, make a difference in people’s lives. 

We have polled extensively on this and it has made me somewhat more optimistic. The polling doesn’t show a country drowning in health misinformation and mistrust on social media.

  • It shows a small group of hard-core disbelievers, but smallish; just 1% believe all of the vaccine myths, for example.  
  • It shows another group who trust the science. Let’s call them the NAM Americans.
  • But most Americans are stuck in the middle, uncertain about what is true and who to believe on almost every key question. They have heard the lies, but they don’t necessarily believe them. They say they don’t believe what they see on social media.

They are “up for grabs.” The situation is far from hopeless. A few hundred thousand or even a million posts on social media are NOT the whole country. Usually, its folks reinforcing views they already hold. And the most trusted messengers are still physicians and nurses and pharmacists – MANY OF YOU. It’s up to us to reach the vast majority in the middle and turn this around. Many of us seek discovery or to fill knowledge gaps in our work. We also need to keep people and relevance centered in everything we do.

Thank you very much for having me and for honoring Victor.

###


Source link